
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
MNK's Log. PSSD Recov 12-18mo 10', PFS recov 11m-16mo 18’. hEDS/AuDHD/Markets.
- Thread starter MNK99
- Start date

MNK99
Well-Known Member
- Messages
- 5,560
Perhaps but IDK. Most the gains I made doing anything in 2018 were permanent. Maybe just exercising a lot keeps sexual health all of it great.
I think I can fix like 1-3 percent of pfs with carnivore and tei (a hell of a lot more with both, like hEDS/Autism, PTSD stuff),
From the old carnivore thread.
I think if Ozeph goes off of i(5.5-6 yrs straight) or that guy that was on Moral Medicine who is 30 something, and did it 3 yrs, 90-95% of their issues remain cured.
IF they went off then went on dutasteride or worse... maybe some more issues would happen. OR if they ate a trash diet (a non bodybuilding diet, non 60-70% clean diet keto, paleo, "balanced" whatever), sure I am sure depression, anxiety and stuff would come back but no penis-brain connection, burning pain, wanting to end life, the full gamut of symptoms on Propecia help? NO.
Weight gain, being far from optimal health? ya.
TEI works really well for some and I was one of them, but I think that is bc of fasting and hardcore exercise and ru, and the electrolyte protocol, and randro/4andro, doing like 95% or more 97% of CD's and like 99% of the good things on here. BY itself, starting on day one tei. I'd probably hate it tbh.
Carnivore in strictly bad health, ya it would have helped me for sure. Easier to convince people and yourself of such a thing when you are weak, look bad, and are ill. When you are just sub optimal it looks more risky, but yeah one week of it destroys juice feasting, and like 21-30 days of breuss fasting (tho that is pretty good too, hard to stick to perhaps, better for ppl with different issues maybe I had copper tox a long time ago and Orion presumably had vit a toxicity. Carnivore is better for me and like avoiding liver and similar foods, maybe breuss fasting is better for him, and low vit a diet, who knows).
Carnivore back in 2017 instead of other shyt would have been way better but water fasting start of 2018 was huge too.
2 weeks of carnivore I probably would be the weight I was at end of 2018 with lifting hardcore... and most muscle restored maybe 2-3 weeks. But yeah I have a much stronger health state.
TEI will be done soon enuff anyways again and fully but in months.
Carnivore a week isn't good enough like fasting 1-2 weeks isn't either for serious toxicity. If you have near perfect health and want to be 7 instead of 9 percent bodyfat, or see what foods you are optimal with (an elimination diet and refeed and trialling and erroring stuff) then fine.
[/HEADING]
Now I do think the carnivore diet could help with things like high cholesterol and insulin sensitivity but by it's self it's not a cure.
------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------
I am quite sure I had all that and way worse water fasting and I am quite sure you could cure diabetes etc... and rare diseases with carnivore. I mean if u go off in xmas every once a yr.. for a week or 2 or a few days, fine. If u go off when u just started, no not fine. Still stay cured.
I felt so cured, I ate some bad foods but knew I had to do something, having carnivore as an option would have eased a lot of anxiety and all. Goose and others did well in TEI
but even Tubzy and co did other stuff besides it. His diet in end cured him, I am sure a bad diet for months on end would hurt his health a bit but 98-99% of pfs would still be gone, making him effectively cured.
I can eat peanut butter, gluten bread, literal poison for me in 2017 and much of it poison in 2008 etc or in teens before that... and still have digestion etc. I am used to peak performance tho, and impairing it or ruining my chances of recovery sets me off stress wise, otherwise it isn't that big a deal. It is a big deal in trying to recover things tho like hEDS/pfs a bit,
PFS is literally a small prob for me. Various steroid/ sarm cycles, test and cialist would work. Test cream and hcg. I am sure. I am also sure.... that it won't do much (it would do some tho for sure, getting stronger) for hEDS. Not sure it would help anxiety, ptsd, depression, autism all that much. SO I hope carnivore does a lot and then tei. I had one cup of coffee no dex in 4 days and had none in 2022 2023 2021 most of it either. not taking dex and giving up on life vs being fitter than all 25 year olds and slaying life and taking it.. isn't a marker of health, as far as I am concerned.
Waking at 4am and trading or studying, working out twice and sleeping naturally 10-11pm for a good amt of time, and eating omad and charming people, with or without dex is better than just not being on it. "Oh u take no meds, you're healthier". No u retard I was just fitness model ripped and healthy and you're too fat, stupid, and lazy to realize what peak performance is for you (and you never had it), let alone me. I am talking to stupid people in my real life and most ppl tbh but not ppl on Hackstasis..
NO longer true, it has cured some people of PFS.
Makes zero sense why TEI would and these things wouldn't. They both can open up the epigenome and let you fix things.
SO can an HDAC inhibitor like Lithium carbonate and test... or lith carbonate or sodium valproate and a hard steroid like DHB.
I wouldn't do the last line or probably not unless I wanted to get results really fast or I was desperate or had less inner strenght. Fasting, carnivore are obviously less dangerous/risky.
I doubt that would fuck me up either tho, but it is probably not a joke either. It is hard, to take sodium valproate and lithium carbonate.
ALL steak, all red meat and water and lifting and later the same or a modified paleo/slow oxi diet and some cooked veg daily to remove metals.... and TEI supplements seems less crazy
than the hardcore bipolar drugs and a riskier steroid like DHB.
I have no doubt that also works, I don't know why tho. Opening up the epigenome again, with an HDAC inhibitor.
TEI can do that too but why would it work optimally in ok health, when I can get in excellent af health and then do it? Like I did in 2018 and like I had till 2022 or so... until neck injury, probably worsened hEDS/HSD and worsened pfs a bit, and the covid vax. I didn't really crash per se, or if I did it was autism/ ptsd like crash more than anything. It was over my perfect life in grasps being ruined. Again by healthcare (lockdowns, quitting medicine that helped DEX and also tei before way before that, and also perfect diet and exercise (then made illegal practically), and the forced vaccine (harmful treatment, not even a vaccine), for no fucking reason).
I think I can fix like 1-3 percent of pfs with carnivore and tei (a hell of a lot more with both, like hEDS/Autism, PTSD stuff),
From the old carnivore thread.
I think if Ozeph goes off of i(5.5-6 yrs straight) or that guy that was on Moral Medicine who is 30 something, and did it 3 yrs, 90-95% of their issues remain cured.
IF they went off then went on dutasteride or worse... maybe some more issues would happen. OR if they ate a trash diet (a non bodybuilding diet, non 60-70% clean diet keto, paleo, "balanced" whatever), sure I am sure depression, anxiety and stuff would come back but no penis-brain connection, burning pain, wanting to end life, the full gamut of symptoms on Propecia help? NO.
Weight gain, being far from optimal health? ya.
TEI works really well for some and I was one of them, but I think that is bc of fasting and hardcore exercise and ru, and the electrolyte protocol, and randro/4andro, doing like 95% or more 97% of CD's and like 99% of the good things on here. BY itself, starting on day one tei. I'd probably hate it tbh.
Carnivore in strictly bad health, ya it would have helped me for sure. Easier to convince people and yourself of such a thing when you are weak, look bad, and are ill. When you are just sub optimal it looks more risky, but yeah one week of it destroys juice feasting, and like 21-30 days of breuss fasting (tho that is pretty good too, hard to stick to perhaps, better for ppl with different issues maybe I had copper tox a long time ago and Orion presumably had vit a toxicity. Carnivore is better for me and like avoiding liver and similar foods, maybe breuss fasting is better for him, and low vit a diet, who knows).
Carnivore back in 2017 instead of other shyt would have been way better but water fasting start of 2018 was huge too.
2 weeks of carnivore I probably would be the weight I was at end of 2018 with lifting hardcore... and most muscle restored maybe 2-3 weeks. But yeah I have a much stronger health state.
TEI will be done soon enuff anyways again and fully but in months.
Carnivore a week isn't good enough like fasting 1-2 weeks isn't either for serious toxicity. If you have near perfect health and want to be 7 instead of 9 percent bodyfat, or see what foods you are optimal with (an elimination diet and refeed and trialling and erroring stuff) then fine.
[/HEADING]
[HEADING=3]Goose12
I think the carnivore diet is good for mid or short term use but it's not a cure. Everyone s symptoms come back as soon as they go off the diet. The only thing that will cure you is detox, tei, dating, ect...I'm really intrigued by this
I follow Victor Pride, bold and determined podcast.
Dude spits so much truth and the way he's describing carnivore diet vs. not doing it reflect my limited experience with it so thinking about trying it
opinions?
I had a big salad and got crazy brainfog/laziness
but with a pure meat meal I did not lose much momentum
Now I do think the carnivore diet could help with things like high cholesterol and insulin sensitivity but by it's self it's not a cure.
------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------
I am quite sure I had all that and way worse water fasting and I am quite sure you could cure diabetes etc... and rare diseases with carnivore. I mean if u go off in xmas every once a yr.. for a week or 2 or a few days, fine. If u go off when u just started, no not fine. Still stay cured.
I felt so cured, I ate some bad foods but knew I had to do something, having carnivore as an option would have eased a lot of anxiety and all. Goose and others did well in TEI
but even Tubzy and co did other stuff besides it. His diet in end cured him, I am sure a bad diet for months on end would hurt his health a bit but 98-99% of pfs would still be gone, making him effectively cured.
I can eat peanut butter, gluten bread, literal poison for me in 2017 and much of it poison in 2008 etc or in teens before that... and still have digestion etc. I am used to peak performance tho, and impairing it or ruining my chances of recovery sets me off stress wise, otherwise it isn't that big a deal. It is a big deal in trying to recover things tho like hEDS/pfs a bit,
PFS is literally a small prob for me. Various steroid/ sarm cycles, test and cialist would work. Test cream and hcg. I am sure. I am also sure.... that it won't do much (it would do some tho for sure, getting stronger) for hEDS. Not sure it would help anxiety, ptsd, depression, autism all that much. SO I hope carnivore does a lot and then tei. I had one cup of coffee no dex in 4 days and had none in 2022 2023 2021 most of it either. not taking dex and giving up on life vs being fitter than all 25 year olds and slaying life and taking it.. isn't a marker of health, as far as I am concerned.
Waking at 4am and trading or studying, working out twice and sleeping naturally 10-11pm for a good amt of time, and eating omad and charming people, with or without dex is better than just not being on it. "Oh u take no meds, you're healthier". No u retard I was just fitness model ripped and healthy and you're too fat, stupid, and lazy to realize what peak performance is for you (and you never had it), let alone me. I am talking to stupid people in my real life and most ppl tbh but not ppl on Hackstasis..
NO longer true, it has cured some people of PFS.
Makes zero sense why TEI would and these things wouldn't. They both can open up the epigenome and let you fix things.
SO can an HDAC inhibitor like Lithium carbonate and test... or lith carbonate or sodium valproate and a hard steroid like DHB.
I wouldn't do the last line or probably not unless I wanted to get results really fast or I was desperate or had less inner strenght. Fasting, carnivore are obviously less dangerous/risky.
I doubt that would fuck me up either tho, but it is probably not a joke either. It is hard, to take sodium valproate and lithium carbonate.
ALL steak, all red meat and water and lifting and later the same or a modified paleo/slow oxi diet and some cooked veg daily to remove metals.... and TEI supplements seems less crazy
than the hardcore bipolar drugs and a riskier steroid like DHB.
I have no doubt that also works, I don't know why tho. Opening up the epigenome again, with an HDAC inhibitor.
TEI can do that too but why would it work optimally in ok health, when I can get in excellent af health and then do it? Like I did in 2018 and like I had till 2022 or so... until neck injury, probably worsened hEDS/HSD and worsened pfs a bit, and the covid vax. I didn't really crash per se, or if I did it was autism/ ptsd like crash more than anything. It was over my perfect life in grasps being ruined. Again by healthcare (lockdowns, quitting medicine that helped DEX and also tei before way before that, and also perfect diet and exercise (then made illegal practically), and the forced vaccine (harmful treatment, not even a vaccine), for no fucking reason).
Last edited:

MNK99
Well-Known Member
- Messages
- 5,560
I had mustard and a tiny bit of hot sauce and yeah.. good. 205-206lb from 210 pre this carnivore stint. this isn't my normal weight... all of sickness i was 166lbs then 198-200lbs no washroom.
I was 198lbs end randro/4andro cycle.. like 190-194 on herbs before and after that.. and on nothing 186-189lbs.. 192lbs for 6mo at least... and then later yeah hella skinnier at 176-183lbs but ripped at all those weights. electrolytes/minerals may have drastic impacts (even from food or retaining them better on say sarms or test) with my connective tissue disorder. It is like you start off weaker than others, but fasting, let alone a tiny bit of gear, you respond 10x better than most people too. So...
People said I was jacked at 18-21 tho. Same people seeing me at 15 or 16, if they only saw me at 9-13 or so, they would never know I was formerly obese.
I do this for me tho.
I like looking like a Tekken Character. I will again. I really need a haircut, because this is looking fucked up rite now. Too long on the sides. Like Javier Bardem in No Country For Old Men, I look mentally unstable. It will be better after I style it and hide a lot on the sides.
--Diet 4d ago perfect
--3d ago perfect
--2d ago perfect
--then a fuck up... some frozen cookie dough, and a bread and peanut butter (poison), bad.
--then yday, cooked organic gmo free, fresh ground lamb. and one tenderloin grilling steak.
--some mustard, tiny tiny bit of hot sauce.
--1.5 servings (a lot of volume) of iced starbucks iced black coffee (store bought), I will make more of my coffee when I can like it more again.
Like when I am ripped af at 190lbs and also when I feel healthier and like I really like it.
--For now this is cool and ok but yeah ...lazy and I usually only like the coffee I order. Jamaican Blue Mountain, Deathwish, Dark Horse coffee from Toronto, etc.
--I can have coffee, and dex.. and still do carnivore perfectly. I will keep hot sauce and mustard (a made up food or derived from pepper, some mustard oil) for 2-3x a month maybe 4-5x a month if I can.
--I ethnically had tea, coffee, and hot sauce/ spicy food and well lamb, sausage, burgers go from boring to delicious with like 2 tea spoons of mustard.
--so then later get raw cheese, raw dairy. Probably use goat milk to make kefir and yogurt. And cheese and buy some pre made goat cheese.
--to buy straight up raw dairy, I am not sure that is allowed here, maybe from farms directly but not at stores (probably that is the case).
--I will learn to make it on my own. Damn. It is probably kind of hard but not that hard.
--I made amazing cavatappi, rice pasta, fillet mignons, cooked veg and like donair quality meats... some guac.,
--now I am only cooking meat.
--so yeah I mean I'd rather buy stuff but making meat and having only pure diet is good.
--I don't and won't feel bad about mustard or hot sauce 30-45x a year, who cares. It is hard to adjust.
--It will keep me from cheating.
--SOME coffee and dex is fine too.
--I want to take test cream to see how much it helps motivation and back and neck pain and ankle pain and so I can cut in 30-45days or 60days to very ripped instead of pretty ripped and more work to do.
--I felt like all self esteem issues, all things were gone. I had loose skin tiny bit stomach half a pound less even, cut it off. extra nip cut it off over 12-13 yrs ago. Hair loss? i mean it will be good till 50 55 60, i can get fues and new meds maybe (welll probably not new hair loss meds, that would be stupid and dangerous),
--beyond normal muscle mass for age and genetics? ya probably 10-12 yrs ago I had more muscle than most ppl of every race except pro bodybuilders and western savanah african genetics.
--some gear for me, i double triple lifts (seemingly not fucking test tho but keep taking it dht should go up a lot. i mean rad probably (too injured to test, too depressed)... and ostarine, lgd, and randro/4andro.
--i mean 300pushups 200 crunches with ease versus like 150- 100 with ease
--i mean back lat pull downs and seated rows 200-250 reps 80 110 120 150 180 210lbs and shyt like that 200 reps
--versus like 140 160lb 170lbs and like 125 150 reps. and injuries.
--all I'm saying is I worked hard for my body and physique and I mean I will get injuries throughout life.
--I am very intelligent and I can't use all of it.
--I may as well use some of the advantages of my disability (insane response to some gear, and great response to stims), to help me fix some of the fucked up parts (injuries, severe ADHD/ probably moderate I am really hoping not severe autism). Use some test, dht, and dex to help joint hypermobility, prevent bone breakages, recover/ recoup from injuries to skeletal muscle/connective tissue, and keep reaching goals.
--And to help discipline, motivation and all.
--SURE IF I can do all that with only carnivore cool. AND only tei after, cool but I mean I am the one who has to have hEDS/HSD forever, it isn't even that bad no girl has ever complained.
--but imagine working out pre work pre eating most of your adult life or at the end of the day, well sort of end after work and school, and then like eating. But now having to wait.
--same time you cannot rush back, neck injures... it takes as long as it takes. Quite certain some sarm and test cream.. rad 3-4mg or dht 5mg-10mg a day.. and test id be fine.
--maybe proper sex drive and function on day 45 50 60, with lifting.
--if all it does is make stronge,r doesn't help sexual function (I am sure it does and it must but it could be better), and make me think about sex more/ be addicted to pron or something, then that's bad.
--I definitely can get addicted to things, so in that sense, I kind of don't want it.
--I think I will not mind wearing braces, and won't need them as much at the gym and if I do, who cares. On dex/coffee I won't care or mind too much. ON test cream while it ups dht, I should still be super confident, but if it takes days or weeks to get there, I wouldn't be surprised either.
I was 198lbs end randro/4andro cycle.. like 190-194 on herbs before and after that.. and on nothing 186-189lbs.. 192lbs for 6mo at least... and then later yeah hella skinnier at 176-183lbs but ripped at all those weights. electrolytes/minerals may have drastic impacts (even from food or retaining them better on say sarms or test) with my connective tissue disorder. It is like you start off weaker than others, but fasting, let alone a tiny bit of gear, you respond 10x better than most people too. So...
People said I was jacked at 18-21 tho. Same people seeing me at 15 or 16, if they only saw me at 9-13 or so, they would never know I was formerly obese.
I do this for me tho.
I like looking like a Tekken Character. I will again. I really need a haircut, because this is looking fucked up rite now. Too long on the sides. Like Javier Bardem in No Country For Old Men, I look mentally unstable. It will be better after I style it and hide a lot on the sides.
--Diet 4d ago perfect
--3d ago perfect
--2d ago perfect
--then a fuck up... some frozen cookie dough, and a bread and peanut butter (poison), bad.
--then yday, cooked organic gmo free, fresh ground lamb. and one tenderloin grilling steak.
--some mustard, tiny tiny bit of hot sauce.
--1.5 servings (a lot of volume) of iced starbucks iced black coffee (store bought), I will make more of my coffee when I can like it more again.
Like when I am ripped af at 190lbs and also when I feel healthier and like I really like it.
--For now this is cool and ok but yeah ...lazy and I usually only like the coffee I order. Jamaican Blue Mountain, Deathwish, Dark Horse coffee from Toronto, etc.
--I can have coffee, and dex.. and still do carnivore perfectly. I will keep hot sauce and mustard (a made up food or derived from pepper, some mustard oil) for 2-3x a month maybe 4-5x a month if I can.
--I ethnically had tea, coffee, and hot sauce/ spicy food and well lamb, sausage, burgers go from boring to delicious with like 2 tea spoons of mustard.
--so then later get raw cheese, raw dairy. Probably use goat milk to make kefir and yogurt. And cheese and buy some pre made goat cheese.
--to buy straight up raw dairy, I am not sure that is allowed here, maybe from farms directly but not at stores (probably that is the case).
--I will learn to make it on my own. Damn. It is probably kind of hard but not that hard.
--I made amazing cavatappi, rice pasta, fillet mignons, cooked veg and like donair quality meats... some guac.,
--now I am only cooking meat.
--so yeah I mean I'd rather buy stuff but making meat and having only pure diet is good.
--I don't and won't feel bad about mustard or hot sauce 30-45x a year, who cares. It is hard to adjust.
--It will keep me from cheating.
--SOME coffee and dex is fine too.
--I want to take test cream to see how much it helps motivation and back and neck pain and ankle pain and so I can cut in 30-45days or 60days to very ripped instead of pretty ripped and more work to do.
--I felt like all self esteem issues, all things were gone. I had loose skin tiny bit stomach half a pound less even, cut it off. extra nip cut it off over 12-13 yrs ago. Hair loss? i mean it will be good till 50 55 60, i can get fues and new meds maybe (welll probably not new hair loss meds, that would be stupid and dangerous),
--beyond normal muscle mass for age and genetics? ya probably 10-12 yrs ago I had more muscle than most ppl of every race except pro bodybuilders and western savanah african genetics.
--some gear for me, i double triple lifts (seemingly not fucking test tho but keep taking it dht should go up a lot. i mean rad probably (too injured to test, too depressed)... and ostarine, lgd, and randro/4andro.
--i mean 300pushups 200 crunches with ease versus like 150- 100 with ease
--i mean back lat pull downs and seated rows 200-250 reps 80 110 120 150 180 210lbs and shyt like that 200 reps
--versus like 140 160lb 170lbs and like 125 150 reps. and injuries.
--all I'm saying is I worked hard for my body and physique and I mean I will get injuries throughout life.
--I am very intelligent and I can't use all of it.
--I may as well use some of the advantages of my disability (insane response to some gear, and great response to stims), to help me fix some of the fucked up parts (injuries, severe ADHD/ probably moderate I am really hoping not severe autism). Use some test, dht, and dex to help joint hypermobility, prevent bone breakages, recover/ recoup from injuries to skeletal muscle/connective tissue, and keep reaching goals.
--And to help discipline, motivation and all.
--SURE IF I can do all that with only carnivore cool. AND only tei after, cool but I mean I am the one who has to have hEDS/HSD forever, it isn't even that bad no girl has ever complained.
--but imagine working out pre work pre eating most of your adult life or at the end of the day, well sort of end after work and school, and then like eating. But now having to wait.
--same time you cannot rush back, neck injures... it takes as long as it takes. Quite certain some sarm and test cream.. rad 3-4mg or dht 5mg-10mg a day.. and test id be fine.
--maybe proper sex drive and function on day 45 50 60, with lifting.
--if all it does is make stronge,r doesn't help sexual function (I am sure it does and it must but it could be better), and make me think about sex more/ be addicted to pron or something, then that's bad.
--I definitely can get addicted to things, so in that sense, I kind of don't want it.
--I think I will not mind wearing braces, and won't need them as much at the gym and if I do, who cares. On dex/coffee I won't care or mind too much. ON test cream while it ups dht, I should still be super confident, but if it takes days or weeks to get there, I wouldn't be surprised either.
Last edited:
MNK99
Well-Known Member
- Messages
- 5,560
If I must choose one recreational drug... and it allows me to live to 95-100 and be healthy. It is stims. some MDMA and cannabis use. Nicotine vaped too.
If I can function well on no alcohol ever (done), and no vaping (done by accident), and no coffee (short times I have done without) and no dex (can and did), then cool.
My tests will be clean regardless as soon as I lift six weeks. I mean endo, blood tests, blood pressure, heart rate etc.
12-20 weeks for sure all tests incl hair tests will be healthy. Diet 40-50% and that and exercise = 95 97% some supps, a stim, and androgen... even better than 100%.
I need to get there again.
Optimize hormones and neurotransmitters, you can lift and do all and be motivated and succeed on nothing..., but I mean nothing will replace amphetamines and dht. I barely ever combined both and have only ever done test and var for days, as a steroid. I worked to gain muscle like 110-120lbs and later 145-155lbs lean probably. Measurements are fucked up if you have a conn tissue disorder let alone lost a lot of weight but believe me if you have 18 vains on both arms, and lots on legs and outlift 99% of ppl at the gym including younger ppl who are on gear, you're pretty fucking fit,
People accused me of steroids well into 2021 2022. I lazed and got depressed and lay down and so gained some weight otherwise, yeah I was the strongest usually or near it at big commercial gyms, a realer gym, and my apartment gym minus you know fucking guys that are 250lbs and lifting 30 years or on lots of gear or 6'5 and 280lbs and that's their life. Top 3-4 for strength for sure. dial shyt in... heal injuries (with stem cells), ya i will be flying again and good enuff for me. I am not trying max deadlift max benchpress.. i work upper and lower or total body ideally. never arms day or abs day or anything like that. I used to when I was younger but it seems like a waste of time, and you hit all that anyways. PLUS maybe I could have visible abs and all that, v taper with some rite gear.
Genetic. my conn tissue disorder. EVEN the ROCK barely has visible abs. He has other shyt tho for sure incl height and insane size lol but on just test and primo or test and dht he would still look great but ya he'd be way smaller than the insane gear and gh he uses. Still he'd be really aesthetic. you are aesthetic enough for women 20-30lbs of muscle ago.. and if no loose skin at 18 rather than surgery at 30, confident enuff always... MINUS career WONT NEED ONE with trading eventually or ill die young not sure.
I can always go to law or other schooling and just DCA into ai coins, gaming coins, and sol and sui and hold and make 500k extra and some yrs 2mn 3mn extra keep offline and loan in defi and be set.
but yeah learning skills would be best for that. maybe train and become a trainer and help people with scoliosis, degen disc disease and all.. i mean i only like teaching some things and it is hard to slow down... and when i am super calm and slowed down i dont feel energized or all that happy... maybe long term carnivore will change this. Maybe tho androgens, and a stim, and fasting and intermittent fasting balances a slow oxi 1 to be near their perfect.
maybe fast oxidizers need more ca and dairy to slow down.
Maybe it is made up pseudoscience, I really don't know. Lots fits me and others here tho. Their descriptions and the tendency towards iron being low maybe, and this and that osteoarthritis
I Will do tei soon enuff. BUT maybe just lift and take test cream. so i can lift daily or near it, have perfect diet, medicate ADHD .. take care of ADHD u take care of hEDS.., take care of that with fitness, you take care of pfs.. u stick to diet.. and tei will fix all. don't medicate, dont eat rite... i mean, what are you doing? wasting time.
SOONER at fitness goals again, sooner I can try hcg or just tei... for pfs.
Will still look good on stims with replaced electrolytes, mg. And b. (I mean if u fast 22-24hrs daily, workout harder than 98% of people... ya i mean you will be mobile).
If we are only talking looks and not executive function, I guess androgens (tho ya my best androgen use was in recomping and preparing for abdominoplasty and after that, in recovering from Fin).
I don't think test and dex automatically means I die at 60 or 50 or even 80-90. I have family members that grew up pre all this modern medicine, didn't take care of catracts, some used to workout like crazy like my Dad's uncle who was 6'1 and a lawyer till 93-94. maybe he wasn't doing fuck all at 91-92 but he technically still had that job lol for the gov't. I imagine he was less efficient/effective at 82 and 79 but ya he isn't meat, diet, and exercise obsessed (THO he was!! He really was diet obsessed but in less optimal ways, and he did calisthenics).
ADD fucking test cream and meat only at 70 or 60 he may have made 95 -99 for all I know. And better self care (like you know actually getting cataracts removed, actually seeing a heart doctor, getting xrays and such, rather than saying "fuck that").
Although yeah I mean.. even at 21-25 I'd be like "fuck that", but that's bc modern health care nearly killed me a ton.
DEX or noots and coffee keep me too smart to be killed by docs and healthcare and pharma.
I think the rite androgens will keep me physically smart and too strong to be screwed too. BUt yeah I mean, you could be 12% bodyfat and 210lbs and look good, this doesn't magically
fix defective collagen, degenerative disc disease.
I am n=1.
I have test cream on my desk, I swear it makes semen better and gives me random erections throughout the day but I also realize that guys like Aztec. Tubzy, Ihatefin and I did lots and in the end Most told me just do TEI. Rwac, Bruschi too, Helen too told me that.
AND in the end I think DIET cured Tubzy.
SO ... I mean just carnivore and some dex, I should be alpha as fuck following it. Really doubt test and dht increases to the upper end of range will make me less alpha but I mean where does it end?
HCG? sure fine. More and more anabolics half or 2/3 of them barely helpful? I will get stronger and more chiselled but I mean which ones cure injury.
ALSO: I am different but I mean if test and rad140 stable cycles help... then in the end it is diet, a weird androgen cycle, and a stim that help me regain life. BUT for PFS only, sure I think Carnivore and TEI are better. AND I did experience mood changes, sleep changes, digestion changes, muscle and water (In a good way, being very lean but I mean 18 18.5 inch arms versus like 1 16.8), I experienced better composition long run after TEI. And better food reactions. BUT I am inclined to think androgens and minerals in general did a lot of that.
I don't need to be so vain. 30 days of carnivore, probably 8.5/10 clear skin. Fix routine and stuff, 9/10.. keep a long time 10/10 skin again.
STAY in a bad loop, yeah I will waste time.
FOR sure I have more erections and better feeling on test cream and dht. BUT randro/4andro were better. I am older now, and I don't think random designer steroids are for me.
--I think ru, hcg, test cream.. test cream and dht cream could work really well for PFS and also for hEDS/HSD.
--I THINK that TEI and carnivore for now, then that and TEI (or just a tei diet or Helen's electrolyte protocol diet, or something different, like Tubzy did but more for slow oxi), I think that will
--cure PFS long run, and also If I am lucky spinal and joint pain and Autism and ADHD from hEDS. Or at least the bad parts of those. Keep the genius moments of Autism and amazing qualities in an emergency and fast thinking and spontenaity and difference in cogntion of ADHD/ASD and that's beyond fine.
--I really doubt taking some test will hurt my tei cycles. I reacted to that and ru better than nearly ev1, possibly ev1.
--Not bragging, I also discontinued perfect recovery and there's certain things I can't do like other people and "normal" people because of ASD/ADHD, and also joint problems.
--AND of course the autism/ADHD made me discontinue the TEI in a sense and get addicted to leverage trading (far less now but yeah I mean if u can make 20-30k usd and turn that into 200k in spot),
--that replaces a lot of jobs... and the only other realistic jobs for me aren't exactly cake walks either (acting, content creation... writing, law? these are not normal things,.., who cares do what makes u happy even if people think they aren't normal, but this is easier said than done when you aren't loaded financially).
--A smart man learns from his mistakes, a wise man learns from others.
-_Same in trading, same in law school, same in recovering from PFS, same in recovering/ treating/managing hEDS/HSD/any disability (cognitive and or physical) disability.
--I want results fast so dex and test cream, with a view to increase DHT and lifting more regularly and strict carnivore sounds amazing ---> strict tei.
--but barely taking coffee and dex and definitely not taking test cream.. and mostly getting results from carnivore and lifting as I get more motivated and recover injury, as hormones and stuff recover
--all naturally, also has its place.
--who is to say 6mo carnivore and 6mo-12mo of tei won't be profoundly life changing? but who is to say, using some androgens won't be better.
--put it this way just some sarms in 2021, I was walking again... despite neck pain. BUT yeah mostly unresearched SAARMs aren't the way. I needed xrays and prolotherapy and got em.
--Test is bioidentical, cream has no excipients, and no oil. Should be safe as fuck. May not work so well tho. Works better than injections I feel.
--I have lasted only 8days on carnivore and like 2 weeks on test injections,... hopefully I make it to 50days 90-180days on carnivore with or without test cream.
--I will tell my GP I am taking dex as needed and coffee and I am adding more of this stuff when I am healthier. I told him about carnivore*, orthomolecular medicine, hair tests, and a lot of the shyt I did
-for pfs years before meeting him , incl chinese and indian herbs (he is Indian I think or close), and yeah we agree it is hard to tell which helped and which are a waste of time for herbs
--but for sure tongkat, fadogia, ashwagandha have research. And some act as serms. And for sure water fasting, ru486, diet and exercise, and the designer steroids i took before had major utility.
--If tubzy finished it off with his diet, then I should be able to with Carnivore. But, I mean we are all vain, of course I'd rather be 190lbs and ripped and less clumsy in 6-8 weeks than 190lbs and ripped in 12-18 weeks, but yeah I mean am I gonna cycle forever?
--IDK and I don't think it is that bad tbh. Low dose cycles long term.
--I listed like 12-15 psyche drugs I tried most were when fucked up with horrid anxiety and autism and untreated ADHD, and were over 18mo in early 20s.
--dex, ritalin... coke nowhere near that. Test cream also isn't.
IF U are fresh and new to pfs I am sure a lot of steroids can be bad but If u literally cut off your loose skin and recomped for years straight, and trained like 10 yrs pre touching gear like me,
and keep many gains forever (i mean years... 5-10yrs and beyond), I mean you are dialled in.
IT is satisfactory to do it with nothing tho. I will try.
Probably the gear that works shows better in me than others. Many complain sarms didn't work or don't work, my physique was better than most those ppl despite supposedly not having great bodybuilding genetics. Mine looked a lot better than most those morons on youtube, including most those gear heads that sell shyt.
BUt Unlike those idiots I did thinks carefully.
EVEN so, not risk free.... and no matter how smart and hard working you are, you cannot magically circumvent / eliminate all risk, incl. how you react to shyt.
IF I never had pfs, I'd still try osta, rad, maybe one of the lgd's, and test. with a test base. No test base, you are asking for trouble. Anavar... primo or mast too.
BUT skipping that and going to only test cream, then supplement with my own purchased (not prescribed but extra) test cream and dht cream... should be good too.
At least there's some research on that. And we can extrapolate things, we may not be able to from sarms.
But yeah not needing fuck all is liberating.
BUT it isn't forever forever. I can fast and lose all my fat.. and water retention.. 2-3 yrs later, i may eat some bad food again (and that outlasts like 99.9% of people. probably more like 10mo and 18mo to be honest, life is stressful. but even that is more discipline than the vast majority of people).
I feel like 10-15mg dex, 100 120-150mg usable test and 4-8x the dht will only help me be more amazing.
AND I doubt the research saying for sure heart disease, damage, death. Same as the anti meat (seventh day adventist vegan cult research).
BUT if u add steroids idk man u will crash lipids and have higher LDL but that is just a marker.
Cut 30lbs I will look like chaffee tho shorter. i mean muscle wise. cut 15-20lbs. but yeah sustainable forever? IDK. keep up some cycles, I will look better.
Maybe I should go find out the exact connective tissue disorder I have but this is kind of like the exact pfs type you have, it is easier in theory than in practice to find out.
(I mean, I probably don't want stims or androgens at all if I have vascular eds, but I mean i'd also be dead a few yrs ago most likely and seriously disabled/handicapped... and yeah I am not).
If I can function well on no alcohol ever (done), and no vaping (done by accident), and no coffee (short times I have done without) and no dex (can and did), then cool.
My tests will be clean regardless as soon as I lift six weeks. I mean endo, blood tests, blood pressure, heart rate etc.
12-20 weeks for sure all tests incl hair tests will be healthy. Diet 40-50% and that and exercise = 95 97% some supps, a stim, and androgen... even better than 100%.
I need to get there again.
Optimize hormones and neurotransmitters, you can lift and do all and be motivated and succeed on nothing..., but I mean nothing will replace amphetamines and dht. I barely ever combined both and have only ever done test and var for days, as a steroid. I worked to gain muscle like 110-120lbs and later 145-155lbs lean probably. Measurements are fucked up if you have a conn tissue disorder let alone lost a lot of weight but believe me if you have 18 vains on both arms, and lots on legs and outlift 99% of ppl at the gym including younger ppl who are on gear, you're pretty fucking fit,
People accused me of steroids well into 2021 2022. I lazed and got depressed and lay down and so gained some weight otherwise, yeah I was the strongest usually or near it at big commercial gyms, a realer gym, and my apartment gym minus you know fucking guys that are 250lbs and lifting 30 years or on lots of gear or 6'5 and 280lbs and that's their life. Top 3-4 for strength for sure. dial shyt in... heal injuries (with stem cells), ya i will be flying again and good enuff for me. I am not trying max deadlift max benchpress.. i work upper and lower or total body ideally. never arms day or abs day or anything like that. I used to when I was younger but it seems like a waste of time, and you hit all that anyways. PLUS maybe I could have visible abs and all that, v taper with some rite gear.
Genetic. my conn tissue disorder. EVEN the ROCK barely has visible abs. He has other shyt tho for sure incl height and insane size lol but on just test and primo or test and dht he would still look great but ya he'd be way smaller than the insane gear and gh he uses. Still he'd be really aesthetic. you are aesthetic enough for women 20-30lbs of muscle ago.. and if no loose skin at 18 rather than surgery at 30, confident enuff always... MINUS career WONT NEED ONE with trading eventually or ill die young not sure.
I can always go to law or other schooling and just DCA into ai coins, gaming coins, and sol and sui and hold and make 500k extra and some yrs 2mn 3mn extra keep offline and loan in defi and be set.
but yeah learning skills would be best for that. maybe train and become a trainer and help people with scoliosis, degen disc disease and all.. i mean i only like teaching some things and it is hard to slow down... and when i am super calm and slowed down i dont feel energized or all that happy... maybe long term carnivore will change this. Maybe tho androgens, and a stim, and fasting and intermittent fasting balances a slow oxi 1 to be near their perfect.
maybe fast oxidizers need more ca and dairy to slow down.
Maybe it is made up pseudoscience, I really don't know. Lots fits me and others here tho. Their descriptions and the tendency towards iron being low maybe, and this and that osteoarthritis
I Will do tei soon enuff. BUT maybe just lift and take test cream. so i can lift daily or near it, have perfect diet, medicate ADHD .. take care of ADHD u take care of hEDS.., take care of that with fitness, you take care of pfs.. u stick to diet.. and tei will fix all. don't medicate, dont eat rite... i mean, what are you doing? wasting time.
SOONER at fitness goals again, sooner I can try hcg or just tei... for pfs.
Will still look good on stims with replaced electrolytes, mg. And b. (I mean if u fast 22-24hrs daily, workout harder than 98% of people... ya i mean you will be mobile).
If we are only talking looks and not executive function, I guess androgens (tho ya my best androgen use was in recomping and preparing for abdominoplasty and after that, in recovering from Fin).
I don't think test and dex automatically means I die at 60 or 50 or even 80-90. I have family members that grew up pre all this modern medicine, didn't take care of catracts, some used to workout like crazy like my Dad's uncle who was 6'1 and a lawyer till 93-94. maybe he wasn't doing fuck all at 91-92 but he technically still had that job lol for the gov't. I imagine he was less efficient/effective at 82 and 79 but ya he isn't meat, diet, and exercise obsessed (THO he was!! He really was diet obsessed but in less optimal ways, and he did calisthenics).
ADD fucking test cream and meat only at 70 or 60 he may have made 95 -99 for all I know. And better self care (like you know actually getting cataracts removed, actually seeing a heart doctor, getting xrays and such, rather than saying "fuck that").
Although yeah I mean.. even at 21-25 I'd be like "fuck that", but that's bc modern health care nearly killed me a ton.
DEX or noots and coffee keep me too smart to be killed by docs and healthcare and pharma.
I think the rite androgens will keep me physically smart and too strong to be screwed too. BUt yeah I mean, you could be 12% bodyfat and 210lbs and look good, this doesn't magically
fix defective collagen, degenerative disc disease.
I am n=1.
I have test cream on my desk, I swear it makes semen better and gives me random erections throughout the day but I also realize that guys like Aztec. Tubzy, Ihatefin and I did lots and in the end Most told me just do TEI. Rwac, Bruschi too, Helen too told me that.
AND in the end I think DIET cured Tubzy.
SO ... I mean just carnivore and some dex, I should be alpha as fuck following it. Really doubt test and dht increases to the upper end of range will make me less alpha but I mean where does it end?
HCG? sure fine. More and more anabolics half or 2/3 of them barely helpful? I will get stronger and more chiselled but I mean which ones cure injury.
ALSO: I am different but I mean if test and rad140 stable cycles help... then in the end it is diet, a weird androgen cycle, and a stim that help me regain life. BUT for PFS only, sure I think Carnivore and TEI are better. AND I did experience mood changes, sleep changes, digestion changes, muscle and water (In a good way, being very lean but I mean 18 18.5 inch arms versus like 1 16.8), I experienced better composition long run after TEI. And better food reactions. BUT I am inclined to think androgens and minerals in general did a lot of that.
I don't need to be so vain. 30 days of carnivore, probably 8.5/10 clear skin. Fix routine and stuff, 9/10.. keep a long time 10/10 skin again.
STAY in a bad loop, yeah I will waste time.
FOR sure I have more erections and better feeling on test cream and dht. BUT randro/4andro were better. I am older now, and I don't think random designer steroids are for me.
--I think ru, hcg, test cream.. test cream and dht cream could work really well for PFS and also for hEDS/HSD.
--I THINK that TEI and carnivore for now, then that and TEI (or just a tei diet or Helen's electrolyte protocol diet, or something different, like Tubzy did but more for slow oxi), I think that will
--cure PFS long run, and also If I am lucky spinal and joint pain and Autism and ADHD from hEDS. Or at least the bad parts of those. Keep the genius moments of Autism and amazing qualities in an emergency and fast thinking and spontenaity and difference in cogntion of ADHD/ASD and that's beyond fine.
--I really doubt taking some test will hurt my tei cycles. I reacted to that and ru better than nearly ev1, possibly ev1.
--Not bragging, I also discontinued perfect recovery and there's certain things I can't do like other people and "normal" people because of ASD/ADHD, and also joint problems.
--AND of course the autism/ADHD made me discontinue the TEI in a sense and get addicted to leverage trading (far less now but yeah I mean if u can make 20-30k usd and turn that into 200k in spot),
--that replaces a lot of jobs... and the only other realistic jobs for me aren't exactly cake walks either (acting, content creation... writing, law? these are not normal things,.., who cares do what makes u happy even if people think they aren't normal, but this is easier said than done when you aren't loaded financially).
--A smart man learns from his mistakes, a wise man learns from others.
-_Same in trading, same in law school, same in recovering from PFS, same in recovering/ treating/managing hEDS/HSD/any disability (cognitive and or physical) disability.
--I want results fast so dex and test cream, with a view to increase DHT and lifting more regularly and strict carnivore sounds amazing ---> strict tei.
--but barely taking coffee and dex and definitely not taking test cream.. and mostly getting results from carnivore and lifting as I get more motivated and recover injury, as hormones and stuff recover
--all naturally, also has its place.
--who is to say 6mo carnivore and 6mo-12mo of tei won't be profoundly life changing? but who is to say, using some androgens won't be better.
--put it this way just some sarms in 2021, I was walking again... despite neck pain. BUT yeah mostly unresearched SAARMs aren't the way. I needed xrays and prolotherapy and got em.
--Test is bioidentical, cream has no excipients, and no oil. Should be safe as fuck. May not work so well tho. Works better than injections I feel.
--I have lasted only 8days on carnivore and like 2 weeks on test injections,... hopefully I make it to 50days 90-180days on carnivore with or without test cream.
--I will tell my GP I am taking dex as needed and coffee and I am adding more of this stuff when I am healthier. I told him about carnivore*, orthomolecular medicine, hair tests, and a lot of the shyt I did
-for pfs years before meeting him , incl chinese and indian herbs (he is Indian I think or close), and yeah we agree it is hard to tell which helped and which are a waste of time for herbs
--but for sure tongkat, fadogia, ashwagandha have research. And some act as serms. And for sure water fasting, ru486, diet and exercise, and the designer steroids i took before had major utility.
--If tubzy finished it off with his diet, then I should be able to with Carnivore. But, I mean we are all vain, of course I'd rather be 190lbs and ripped and less clumsy in 6-8 weeks than 190lbs and ripped in 12-18 weeks, but yeah I mean am I gonna cycle forever?
--IDK and I don't think it is that bad tbh. Low dose cycles long term.
--I listed like 12-15 psyche drugs I tried most were when fucked up with horrid anxiety and autism and untreated ADHD, and were over 18mo in early 20s.
--dex, ritalin... coke nowhere near that. Test cream also isn't.
IF U are fresh and new to pfs I am sure a lot of steroids can be bad but If u literally cut off your loose skin and recomped for years straight, and trained like 10 yrs pre touching gear like me,
and keep many gains forever (i mean years... 5-10yrs and beyond), I mean you are dialled in.
IT is satisfactory to do it with nothing tho. I will try.
Probably the gear that works shows better in me than others. Many complain sarms didn't work or don't work, my physique was better than most those ppl despite supposedly not having great bodybuilding genetics. Mine looked a lot better than most those morons on youtube, including most those gear heads that sell shyt.
BUt Unlike those idiots I did thinks carefully.
EVEN so, not risk free.... and no matter how smart and hard working you are, you cannot magically circumvent / eliminate all risk, incl. how you react to shyt.
IF I never had pfs, I'd still try osta, rad, maybe one of the lgd's, and test. with a test base. No test base, you are asking for trouble. Anavar... primo or mast too.
BUT skipping that and going to only test cream, then supplement with my own purchased (not prescribed but extra) test cream and dht cream... should be good too.
At least there's some research on that. And we can extrapolate things, we may not be able to from sarms.
But yeah not needing fuck all is liberating.
BUT it isn't forever forever. I can fast and lose all my fat.. and water retention.. 2-3 yrs later, i may eat some bad food again (and that outlasts like 99.9% of people. probably more like 10mo and 18mo to be honest, life is stressful. but even that is more discipline than the vast majority of people).
I feel like 10-15mg dex, 100 120-150mg usable test and 4-8x the dht will only help me be more amazing.
AND I doubt the research saying for sure heart disease, damage, death. Same as the anti meat (seventh day adventist vegan cult research).
BUT if u add steroids idk man u will crash lipids and have higher LDL but that is just a marker.
Cut 30lbs I will look like chaffee tho shorter. i mean muscle wise. cut 15-20lbs. but yeah sustainable forever? IDK. keep up some cycles, I will look better.
Maybe I should go find out the exact connective tissue disorder I have but this is kind of like the exact pfs type you have, it is easier in theory than in practice to find out.
(I mean, I probably don't want stims or androgens at all if I have vascular eds, but I mean i'd also be dead a few yrs ago most likely and seriously disabled/handicapped... and yeah I am not).
Last edited:
MNK99
Well-Known Member
- Messages
- 5,560
---

Neuropsychiatr Dis Treat. 2021; 17: 379–388.
Published online 2021 Feb 10. doi: 10.2147/NDT.S290494
PMCID: PMC7882457
PMID: 33603376
Author information Article notes Copyright and License information PMC Disclaimer
Go to:
Keywords: ADHD, autism spectrum disorder, children, hypermobility spectrum disorder, Ehlers-Danlos syndrome
Go to:
Hypermobility is a clinical sign that shows that the range of motion in one or more joints is greater than is considered normal. If the diagnostic criteria for hEDS are not fulfilled but hypermobility is present, the condition may often be classified as a hypermobile spectrum disorder (HSD).1 HSD and hEDS are both characterized by generalized hypermobility in combination with pain, impaired proprioception, and pronounced fatigue.2
There is insufficient knowledge of the underlying mechanisms of pain and fatigue experienced by children with HSD or hEDS. Effective treatments are lacking for this patient group, and a recent meta-analysis has shown that most interventions lack efficacy to improve the functioning of these children.3,4 They also risk developing chronic pain and suffering exclusion in society.5,6 Children with HSD or hEDS show lower self-reported health-related quality of life compared to healthy children, which has been found to be associated with their pain and fatigue.7 A recently published retrospective study has shown that patients with EDS and those with HSD share a common psychiatric presentation.8
In everyday clinical practice, we have observed several patient cases with difficult-to-treat pain or pain syndrome (both with and without hypermobility) in whom the pain problems have almost completely regressed since the patient received a diagnosis of attention-deficit/hyperactivity disorder (ADHD) and received treatment with central nervous system (CNS) stimulant drugs, such as methylphenidate. Clinically, there is also a clear overrepresentation of behavioral problems and hyperactivity, as well as autistics traits, in children with HSD or hEDS. This has aroused our interest to explore in more detail the relationship between HSD or hEDS on the one hand and ADHD or autism spectrum disorder (ASD) on the other.
There are several studies suggesting that hEDS and HSD may be associated with ADHD, though ADHD appears to be more common with HSD than with EDS.8 There is also increasing evidence that ASD is more common in individuals with joint hypermobility-related disorders than expected by chance.9 A Swedish national registry study has recently shown that there is a positive association between EDS and ASD or ADHD, and similar results have been observed for HSD.10
Both ADHD and ASD are neurodevelopmental disorders,9,11 which accounts for their similarities as well as for the differences among them. A recent study by Berenguer et al showed that children with ASD (ASD alone or in co-occurrence with ADHD) showed worse theory of mind skills than children with ADHD, while children with ADHD symptomatology (ADHD alone or with co-occurring ASD) had a more extensive profile of executive functions (EF) deficits than children with ASD only.12 Findings obtained by Craig et al, in their systematic review of EF deficit in ASD and ADHD, are in line with the criteria of the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, where these two neurodevelopmental disorders are no longer mutually exclusive. Authors have concluded, based on neurocognitive endophenotype, that rather than a separate condition with distinct impairments, it seems that the common co-occurence of EF deficit reflects an additive comorbidity.13
The etiology of ADHD is not yet completely understood11,14 and most cases of ASD are of unknown cause.9 Thus, it is not surprising that accepted theories about the underlying mechanisms for relationships between hEDS or HSD and these neurodevelopmental disorders are lacking. Baeza-Velasco et al recently published an explanatory model with at least four different but not mutually exclusive pathways, showing the possible relationships between ADHD and hypermobility: (1) impaired proprioception and, consequently, situations where maintaining motor competences may overload executive functions and attention; (2) musculoskeletal pain that may directly affect attention and concentration; (3) a link between dysautonomia (which is over-represented in HSD and hEDS) and cognitive difficulties; and (4) ADHD and hypermobility having different expressions with a common genetic background.11
Based on these issues and our clinical experience, in this medical records study we wanted to explore our hypothesis that children with HSD or hEDS have a greater risk of developing ADHD and ASD than the normal population. The Ehlers-Danlos diagnostic criteria were changed in 2017 but we presume that the results of our retrospective study can be relevant to future clinical work because, for example, one study found a similar frequency of comorbidities of hEDS (such as gastrointestinal dysfunction and psychological comorbidities) in those patients who met the new criteria and those who did not.15
Go to:
A review of all 201 medical records (113 with hypermobility syndrome and 88 with EDS) was conducted, and the following variables were recorded: gender, age, place of residence, diagnosis, age at diagnosis, Beighton hypermobility score, fatigue, pain, sleep problems, snoring, sleep apnea, continuous positive airway pressure (CPAP) treatment, abdominal pain, constipation, diarrhea, reflux, gastritis, nausea, nutritional problems in childhood, urinary tract problems, ADHD, age at ADHD diagnosis, pharmacological treatment for ADHD, suspected ADHD, autism, Asperger’s syndrome, fulfilment of the old Villefranche criteria for EDS hypermobility type (EDS-ht) from 1997,17 and fulfilment of the new criteria for hEDS from 2017.18,19 Because our registry data predated this change in 2017, we have used the older EDS-ht as a proxy for the newer diagnosis hEDS, as described by the International Consortium on the Ehlers-Danlos Syndromes.2 We also equate the older hypermobility syndrome with its replacement HSD, in accordance with the 2017 nomenclature changes. Concerning neuropsychiatric symptoms, we equate the registered diagnoses of autism and Asperger’s syndrome with the umbrella diagnosis ASD, in accordance with the nomenclature change in 2013 in the DSM-5.20 The children in our study were subdivided in two groups based on the diagnosis from the medical records. Thus, in the first group (HSD group) we have 113 children with M35.7 Hypermobility syndrome while in the other group (hEDS group) we have children with Q79.6 Ehlers-Danlos syndrome. None of the children had been diagnosed with, or exhibited symptoms of, any of the rare forms of EDS, such as vascular EDS. Four children were re-examined for classical EDS or classical-like EDS but did not meet the diagnostic criteria. This allowed us to classify all the 88 EDS cases as hEDS, since we equate EDS-ht with hEDS.
The choice of targeting key symptoms (fatigue, pain, sleep problems, gastrointestinal symptoms, urinary tract problems, and neuropsychiatric symptoms) was based on clinical experience with the patient group in the study.
The total number of children in each age group in Skaraborg was obtained through Statistics Sweden, SCB, and in total there were 38,901 children in the age group 6–18 years.21 The proportion of children with an ADHD diagnosis in Skaraborg was obtained through a register search from the computerized records system.
The Beighton hypermobility scale is a nine-point scale with scores for the presence of any of the following: (a) palmar flexion of the wrist and flexion of the thumb to the volar side of the forearm (one point for each hand), (b) passive dorsal flexion of the little finger more than 90° (one point for each hand), (c) hyperextension of the elbow more than 10° (one point for each arm), (d) hyperextension of the knee joints more than 10° (one point for each leg), and (e) back flexion with legs straight and palms on the floor.19
Neuropsychiatr Dis Treat. 2021; 17: 379–388.
Published online 2021 Feb 10. doi: 10.2147/NDT.S290494
PMCID: PMC7882457
PMID: 33603376
Prevalence of ADHD and Autism Spectrum Disorder in Children with Hypermobility Spectrum Disorders or Hypermobile Ehlers-Danlos Syndrome: A Retrospective Study
Erik Kindgren,1,2 Antonia Quiñones Perez,1 and Rajna Knez1,3Author information Article notes Copyright and License information PMC Disclaimer
Go to:
Abstract
Introduction
Hypermobility spectrum disorders (HSD) and hypermobile Ehlers-Danlos syndrome (hEDS) are both characterized by generalized hypermobility, in combination with pain, affected proprioception, and pronounced fatigue. Clinical observation indicates that behavioral problems, hyperactivity, and autistic traits are overrepresented in children with those conditions. The purpose of this retrospective study was to establish the prevalence of attention-deficit/hyperactivity disorder (ADHD) and autism spectrum disorder (ASD) among children with HSD and hEDS treated in our clinic since 2012.Subjects and Methods
Since Ehlers-Danlos syndrome (EDS) diagnostic criteria and international classification were changed in 2017, we equate the older diagnosis EDS hypermobility type with the newer hEDS and the older hypermobility syndrome with HSD. A registry search from the computerized medical record system found 201 children (88 boys, 113 girls) aged 6–18 years who were treated at our pediatrics department with the diagnoses HSD or EDS. All medical records (113 with HSD, 88 with EDS) were reviewed, and key symptoms such as fatigue and pain, as well as diagnosis of ADHD/ASD, were recorded.Results
All EDS cases could be classified as hEDS. Of the entire study cohort, 16% had a verified ADHD diagnosis and a further 7% were undergoing ADHD diagnostic investigation. Significantly more children with hEDS had ADHD compared to children with HSD (p=0.02). In the age group 15–16 years, 35% of those with hEDS had ADHD and, among those aged 17–18 years, ADHD was present in 46%. Children with coexisting ADHD showed a significantly higher proportion of associated symptoms such as fatigue, sleep-problems, and urinary tract problems. ASD had been verified in 6% of the children. Of those with ASD, 92% had sleep problems.Conclusion
This study shows a strong association between HSD or hEDS and ADHD or ASD. Therefore, children with HSD or hEDS may need to be routinely screened for neuropsychiatric symptoms.Keywords: ADHD, autism spectrum disorder, children, hypermobility spectrum disorder, Ehlers-Danlos syndrome
Go to:
Introduction
There are 13 different diseases known as Ehlers-Danlos Syndrome (EDS), which usually creates misunderstanding for both patients and healthcare professionals. Twelve of the diseases in the EDS group have verified genetics and are very rare, such as classical EDS (prevalence: 5 per 100,000) and vascular EDS (prevalence: 2–3 per 1,000,000).1 For hypermobile EDS (hEDS), a genetic cause has not yet been verified, and this disease is much more common than other EDS subtypes. The prevalence of hEDS may be at least 10 per 100,0001 but the reported figure varies in different studies. Several recent data sources indicate a prevalence from 0.75–2%, and even up to 3.4% in the study to provide a quantification, using joint hypermobility and widespread pain as a proxy for hEDS.2Hypermobility is a clinical sign that shows that the range of motion in one or more joints is greater than is considered normal. If the diagnostic criteria for hEDS are not fulfilled but hypermobility is present, the condition may often be classified as a hypermobile spectrum disorder (HSD).1 HSD and hEDS are both characterized by generalized hypermobility in combination with pain, impaired proprioception, and pronounced fatigue.2
There is insufficient knowledge of the underlying mechanisms of pain and fatigue experienced by children with HSD or hEDS. Effective treatments are lacking for this patient group, and a recent meta-analysis has shown that most interventions lack efficacy to improve the functioning of these children.3,4 They also risk developing chronic pain and suffering exclusion in society.5,6 Children with HSD or hEDS show lower self-reported health-related quality of life compared to healthy children, which has been found to be associated with their pain and fatigue.7 A recently published retrospective study has shown that patients with EDS and those with HSD share a common psychiatric presentation.8
In everyday clinical practice, we have observed several patient cases with difficult-to-treat pain or pain syndrome (both with and without hypermobility) in whom the pain problems have almost completely regressed since the patient received a diagnosis of attention-deficit/hyperactivity disorder (ADHD) and received treatment with central nervous system (CNS) stimulant drugs, such as methylphenidate. Clinically, there is also a clear overrepresentation of behavioral problems and hyperactivity, as well as autistics traits, in children with HSD or hEDS. This has aroused our interest to explore in more detail the relationship between HSD or hEDS on the one hand and ADHD or autism spectrum disorder (ASD) on the other.
There are several studies suggesting that hEDS and HSD may be associated with ADHD, though ADHD appears to be more common with HSD than with EDS.8 There is also increasing evidence that ASD is more common in individuals with joint hypermobility-related disorders than expected by chance.9 A Swedish national registry study has recently shown that there is a positive association between EDS and ASD or ADHD, and similar results have been observed for HSD.10
Both ADHD and ASD are neurodevelopmental disorders,9,11 which accounts for their similarities as well as for the differences among them. A recent study by Berenguer et al showed that children with ASD (ASD alone or in co-occurrence with ADHD) showed worse theory of mind skills than children with ADHD, while children with ADHD symptomatology (ADHD alone or with co-occurring ASD) had a more extensive profile of executive functions (EF) deficits than children with ASD only.12 Findings obtained by Craig et al, in their systematic review of EF deficit in ASD and ADHD, are in line with the criteria of the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, where these two neurodevelopmental disorders are no longer mutually exclusive. Authors have concluded, based on neurocognitive endophenotype, that rather than a separate condition with distinct impairments, it seems that the common co-occurence of EF deficit reflects an additive comorbidity.13
The etiology of ADHD is not yet completely understood11,14 and most cases of ASD are of unknown cause.9 Thus, it is not surprising that accepted theories about the underlying mechanisms for relationships between hEDS or HSD and these neurodevelopmental disorders are lacking. Baeza-Velasco et al recently published an explanatory model with at least four different but not mutually exclusive pathways, showing the possible relationships between ADHD and hypermobility: (1) impaired proprioception and, consequently, situations where maintaining motor competences may overload executive functions and attention; (2) musculoskeletal pain that may directly affect attention and concentration; (3) a link between dysautonomia (which is over-represented in HSD and hEDS) and cognitive difficulties; and (4) ADHD and hypermobility having different expressions with a common genetic background.11
Based on these issues and our clinical experience, in this medical records study we wanted to explore our hypothesis that children with HSD or hEDS have a greater risk of developing ADHD and ASD than the normal population. The Ehlers-Danlos diagnostic criteria were changed in 2017 but we presume that the results of our retrospective study can be relevant to future clinical work because, for example, one study found a similar frequency of comorbidities of hEDS (such as gastrointestinal dysfunction and psychological comorbidities) in those patients who met the new criteria and those who did not.15
Go to:
Materials and Methods
A registry search from the computerized medical record system covering the period from 2012 to 2018 found 201 children aged 6–18 years who were treated at the pediatric and youth medicine clinic at Skaraborg Hospital, Sweden, with the diagnoses Q79.6 Ehlers-Danlos syndrome or M35.7 Hypermobility syndrome (ICD-10).16A review of all 201 medical records (113 with hypermobility syndrome and 88 with EDS) was conducted, and the following variables were recorded: gender, age, place of residence, diagnosis, age at diagnosis, Beighton hypermobility score, fatigue, pain, sleep problems, snoring, sleep apnea, continuous positive airway pressure (CPAP) treatment, abdominal pain, constipation, diarrhea, reflux, gastritis, nausea, nutritional problems in childhood, urinary tract problems, ADHD, age at ADHD diagnosis, pharmacological treatment for ADHD, suspected ADHD, autism, Asperger’s syndrome, fulfilment of the old Villefranche criteria for EDS hypermobility type (EDS-ht) from 1997,17 and fulfilment of the new criteria for hEDS from 2017.18,19 Because our registry data predated this change in 2017, we have used the older EDS-ht as a proxy for the newer diagnosis hEDS, as described by the International Consortium on the Ehlers-Danlos Syndromes.2 We also equate the older hypermobility syndrome with its replacement HSD, in accordance with the 2017 nomenclature changes. Concerning neuropsychiatric symptoms, we equate the registered diagnoses of autism and Asperger’s syndrome with the umbrella diagnosis ASD, in accordance with the nomenclature change in 2013 in the DSM-5.20 The children in our study were subdivided in two groups based on the diagnosis from the medical records. Thus, in the first group (HSD group) we have 113 children with M35.7 Hypermobility syndrome while in the other group (hEDS group) we have children with Q79.6 Ehlers-Danlos syndrome. None of the children had been diagnosed with, or exhibited symptoms of, any of the rare forms of EDS, such as vascular EDS. Four children were re-examined for classical EDS or classical-like EDS but did not meet the diagnostic criteria. This allowed us to classify all the 88 EDS cases as hEDS, since we equate EDS-ht with hEDS.
The choice of targeting key symptoms (fatigue, pain, sleep problems, gastrointestinal symptoms, urinary tract problems, and neuropsychiatric symptoms) was based on clinical experience with the patient group in the study.
The total number of children in each age group in Skaraborg was obtained through Statistics Sweden, SCB, and in total there were 38,901 children in the age group 6–18 years.21 The proportion of children with an ADHD diagnosis in Skaraborg was obtained through a register search from the computerized records system.
The Beighton hypermobility scale is a nine-point scale with scores for the presence of any of the following: (a) palmar flexion of the wrist and flexion of the thumb to the volar side of the forearm (one point for each hand), (b) passive dorsal flexion of the little finger more than 90° (one point for each hand), (c) hyperextension of the elbow more than 10° (one point for each arm), (d) hyperextension of the knee joints more than 10° (one point for each leg), and (e) back flexion with legs straight and palms on the floor.19
e with EDS or HSD’ is not helpful.
MNK99
Well-Known Member
- Messages
- 5,560
Statistical Analysis
The normal distribution for independent variables was analyzed both graphically and with the Shapiro–Wilk test and then Levene’s test for equal variance. The chi-squared test was used to compare categorical variables (gender and symptoms) between the diagnostic groups. t-tests were used to compare continuous variables (age and scores on the Beighton hypermobility scale) between gender and diagnostic groups. The statistics were calculated using SPSS Statistics for Windows, version 25.0 (IBM Corp., Armonk, NY, USA).Ethical Considerations
The study was performed in accordance with the Declaration of Helsinki and was approved by the Regional Ethical Review Board of Western Sweden (approval number 998–18). Due to the retrospective design and lack of study-related interventions, written informed consent was waived. All patient data accessed for the purposes of this investigation complied with relevant data protection and privacy regulations.Go to:
Results
A diagnosis of EDS was noted in 88 of 201 children and a diagnosis of hypermobility syndrome (here classified as HSD) in 113 of 201 (see Table 1). All of the EDS cases could be classified as hEDS because none of these children had been diagnosed with, or exhibited symptoms of, any of the rare forms of EDS.Table 1
Study Population: Age, Gender, and Distribution of Associated Symptoms in Each Diagnosis Group| All | HSD | hEDS | p-value | |
|---|---|---|---|---|
| n=201 | n=113 | n=88 | ||
| Gender | ||||
| Boys, n (%) | 88 (44%) | 47 (42%) | 41 (47%) | 0.479 |
| Girls, n (%) | 113 (56%) | 66 (58%) | 47 (53%) | |
| Age, years | ||||
| All, mean (SD) | 12.0 (3.5) | 12.0 (3.5) | 12.1 (3.7) | 0.871 |
| Boys, mean (SD) | 11.5 (3.4) | 11.3 (3.7) | 11.8 (3.1) | 0.491 |
| Girls, mean (SD) | 12.5 (3.6) | 12.5 (3.2) | 12.4 (4.1) | 0.807 |
| Boys vs girls | p = 0.059 | p = 0.056 | p = 0.453 | |
| Age at diagnosis, years | ||||
| All, mean (SD) | 7.88 (3.79) | 8.27 (3.68) | 7.84 (3.97) | 0.095 |
| Boys, mean (SD) | 6.82 (2.92) | 6.79 (2.80) | 6.85 (3.08) | 0.916 |
| Girls, mean (SD) | 8.71 (4.19) | 9.33 (3.88) | 7.83 (4.47) | 0.059 |
| Boys vs girls | p < 0.001 | p < 0.001 | p = 0.162 | |
| Pain, n (%) | 156 (78%) | 85 (76%) | 71 (81%) | 0.417 |
| Fatigue, n (%) | 114 (57%) | 52 (46%) | 62 (71%) | 0.001 |
| Sleep-related symptoms | ||||
| Sleep problems, n (%) | 91 (45%) | 45 (40%) | 46 (52%) | 0.079 |
| Snoring, n (%) | 6 (3%) | 3 (3%) | 3 (3%) | 0.755 |
| Sleep apnea, n (%) | 9 (5%) | 3 (3%) | 6 (7%) | 0.157 |
| CPAP treatment, n (%) | 2 (1%) | 0 (0%) | 2 (2%) | 0.107 |
| Gastrointestinal symptoms | ||||
| Presence of at least one symptom, n (%) | 119 (52%) | 61 (54%) | 58 (66%) | 0.088 |
| Abdominal pain, n (%) | 52 (26%) | 28 (25%) | 24 (27%) | 0.689 |
| Constipation, n (%) | 85 (42%) | 43 (38%) | 42 (48%) | 0.168 |
| Reflux/gastritis, n (%) | 35 (17%) | 17 (15%) | 18 (21%) | 0.316 |
| Diarrhea, n (%) | 6 (3%) | 4 (4%) | 2 (2%) | 0.600 |
| Nutrition problems during childhood, n (%) | 5 (3%) | 1 (1%) | 4 (5%) | 0.098 |
| Urinary tract problems, n (%) | 27 (13%) | 11 (10%) | 16 (18%) | |
| Neuropsychiatric symptoms | ||||
| ADHD verified/diagnosed, n (%) | 32 (16%) | 12 (11%) | 20 (23%) | 0.020 |
| ADHD under investigation/suspected, n (%) | 14 (7%) | 11 (10%) | 3 (3%) | 0.081 |
| ASD, n (%) | 13 (6%) | 5 (4%) | 7 (8%) | 0.295 |
| Beighton hypermobility score | ||||
| All, mean (SD) | 4.92 (1.96) | 4.67 (1.85) | 5.23 (2.06) | 0.052 |
| Boys, mean (SD) | 4.79 (2.02) | 4.42 (1.84) | 5.21 (2.15) | 0.079 |
| Girls, mean (SD) | 5.01 (1.91) | 4.84 (1.85) | 5.25 (1.99) | 0.279 |
| Boys vs girls | p = 0.451 | p = 0.245 | p = 0.922 |
Notes: t-tests were used for comparisons of continuous variables and chi-squared tests for categorical variables; Bold text indicates a statistically significant difference with a p-value less than 0.05.
Abbreviations: HSD, hypermobility spectrum disorders; hEDS, hypermobile Ehlers-Danlos syndrome; ASD, autism spectrum disorders, includes Asperger’s syndrome.
The gender distribution in the whole group was 44% boys and 56% girls. The hEDS group had a relatively even gender distribution of 47% boys and 53% girls, but in the HSD group there was a slightly skewed distribution: 42% boys and 58% girls. The mean age at diagnosis was 7.9 years. In the hEDS group, boys received their diagnosis just over two years earlier than girls (p < 0.001), and boys in the HSD group received the diagnosis just over one year earlier than the girls (p < 0.001).
Pain and Fatigue
Pain was noted in 78% of all children, but without significant differences between diagnosis groups. Fatigue was noted in 71% of children in the hEDS group and 46% of those in the HSD group, a statistically significant difference (p = 0.001) (Table 1).Sleep-Related Symptoms
In the entire study cohort, 45% had some sleep-related symptoms in the form of sleep problems, snoring, or verified sleep apnea. There were no significant differences between diagnosis groups (Table 1).Gastrointestinal Symptoms
In the entire study cohort, 52% had some form of gastrointestinal symptoms: abdominal pain, constipation, reflux, gastritis, diarrhea, or nutritional problems. There were no significant differences between diagnosis groups (Table 1).Neuropsychiatric Symptoms
A verified ADHD diagnosis was found in 16% of the children, while another 7% were under ADHD assessment or suspected ADHD was mentioned in their records. An ADHD diagnosis was significantly more common in the hEDS group, where 23% had a verified diagnosis, than in the HSD group, where 11% had ADHD diagnosis (p = 0.020). In the age group 15–16 years, 35% (13 of 37) of those with hEDS or HSD had an ADHD diagnosis, and in the age group 17–18 years it was 46% (11 of 24). The mean age at which patients in the hEDS group received their ADHD diagnosis was 9.2 years, while in the HSD group this was 9.9 years.From the total sample, 152 of 201 children were resident in our catchment area. A verified ADHD diagnosis was found in 20% (30 of 152) of those children, while another 7% (11 of 152) were under ADHD assessment, or suspected ADHD was mentioned in their records. This is a significantly higher proportion than in the normal population (usually about 5%),11 and significantly higher (p < 0.001) compared to all children aged 6–18 years in our catchment area (Skaraborg), where during the period 2015–2018, 5.8% had an ADHD diagnosis. In the age group 17–18, 47% of the children with hEDS or HSD in our catchment area had an ADHD diagnosis.
In the entire cohort, 6.5% (13 of 201), and in our catchment area 7.2% (11 of 152), had a verified diagnosis of autism or Asperger’s syndrome in their medical records (reclassified here as ASD). This was a significantly higher proportion (p < 0.001) compared to all children aged 6–18 years in our catchment area, where 2.6% have been diagnosed with ASD.
Associated Symptoms in Children with Neurodevelopmental Disorders
Children with a verified ADHD diagnosis generally showed a higher proportion of associated symptoms compared to children who did not have an ADHD diagnosis (see Figure 1). In the entire study cohort, fatigue (p < 0.001), sleep problems (p < 0.001), and urinary tract problems (p < 0.05) were significantly higher in those with a verified ADHD diagnosis. No significant difference in the proportion with pain or other gastrointestinal symptoms was detected, but a tendency towards a higher incidence of reflux/gastritis was detected in those with an ADHD diagnosis than those without (p = 0.054) (Figure 1). In addition, sleep problems were overrepresented in the group of 14 children undergoing ADHD assessment (71% vs 36%, p = 0.001). In the HSD group, significantly more fatigue (p < 0.001), sleep problems (p < 0.001), and reflux/gastritis (p = 0.036) were found in those with an ADHD diagnosis. In the hEDS group, significantly more sleep problems (p = 0.047) and urinary tract problems (p = 0.020) were found in those with an ADHD diagnosis.[IMG alt="An external file that holds a picture, illustration, etc.
Object name is NDT-17-379-g0001.jpg"]https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7882457/bin/NDT-17-379-g0001.jpg[/IMG]
Figure 1
Percentage of associated symptoms in 201 children with HSD or hEDS, comparing those with and without a diagnosis of ADHD. Analyzed with chi-squared tests. *p<0.05; **p<0.001.
Abbreviations: ADHD, attention-deficit/hyperactivity disorder; HSD, hypermobility spectrum disorders; hEDS, hypermobile Ehlers-Danlos syndrome.
Of those children with an ADHD diagnosis, 56% (18 of 32) had ongoing treatment with CNS stimulants. Comparing the children with ADHD who had this treatment and those who did not, no significant differences were detected for the symptoms sleep problems and pain, but there was a tendency toward fewer sleep problems in the treated group.
Of the children with ASD, 92% had sleep disorders, and this was significantly higher than in those without ASD (p < 0.001) (Figure 2). There were also significant differences in fatigue where the presence was higher among children with coexisting ASD than in those without it (p < 0.05).
[IMG alt="An external file that holds a picture, illustration, etc.
Object name is NDT-17-379-g0002.jpg"]https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7882457/bin/NDT-17-379-g0002.jpg[/IMG]
Figure 2
Percentage of associated symptoms in 201 children with HSD or hEDS, comparing those with and without a diagnosis of ASD. Analyzed with chi-squared tests. *p<0.05; **p<0.001.
Abbreviations: ASD, autism spectrum disorders; HSD, hypermobility spectrum disorders; hEDS, hypermobile Ehlers-Danlos syndrome.
Beighton Hypermobility Score
There were no significant gender differences in Beighton scores, but the higher scores in the hEDS group than the HSD group approached statistical significance (p = 0.052) (Table 1).For both the hEDS and HSD group, the scores on the Beighton scale were generally slightly higher, but not significantly so, for children with associated symptoms (fatigue, pain, sleep problems, snoring, sleep apnea, CPAP treatment, gastrointestinal symptoms, urinary tract problems, ADHD, and suspected ADHD). Those with ASD had significantly higher Beighton scores (6.22 vs 4.80 points, p = 0.035).
Go to:
MNK99
Well-Known Member
- Messages
- 5,560
Discussion
The purpose of this register study was to examine whether the clinically observed association between HSD or hEDS and neuropsychiatric symptoms can also be statistically confirmed. The results show that 16% of children with HSD or hEDS also have a verified ADHD diagnosis, which is more than three times higher than the expected rate (about 5%).11 The rate of ASD among children with HSD or hEDS was also higher, approximately twice the expected rate. The children with neuropsychiatric symptoms or diagnose also had a higher proportion of associated symptoms, in particular fatigue, sleep disorders, and urinary tract problems. However, they did not have more pain.Boys with HSD or hEDS were diagnosed on average two years earlier than girls, which is well in line with our clinical experience, where we often see boys having the most symptoms before puberty. The problems in the musculoskeletal system then decrease during puberty, probably due to increased muscle mass. A large proportion of the girls do not seek medical care until puberty, when the symptoms and consequent problems seem to increase. The mean age at first HSD/hEDS diagnosis for all our study population is 7.88 years (SD 3.79), with 6.82 (SD 2.92) for boys and 8.71 (SD 4.19) for girls. Results for the boys in our sample are in line with the recently published cohort study where the age at first joint hypermobility syndrome (JHS)/EDS diagnosis peaked in the age group 5–9 years for a male. In contrary, data from our sample show that girls, although diagnosed significantly later than boys, get diagnosis even sooner than in this cohort study where age at first diagnosis peaked in the age group 15–19 years for a female.22
In our study, the proportion of children with an ADHD diagnosis was significantly higher in the older age groups, with a verified ADHD diagnosis in almost half of those aged 17–18 (compared to 15% of all children aged 17–18 in our catchment area). Several studies have reported high prevalence of generalized joint hypermobility in patients with attention deficit disorder (ADD) or ADHD,23 while only a few studies investigate the presence of ADHD in patient with EDS-ht and JHS or hypermobility syndrome. Thus, Castori et al have found that ADHD was present in 34.8% (8 out of the 23) of the patient with JHS/EDS-ht.24 Although this was a higher prevalence than in our study, it is important to underline that the majority of the whole study population (n=82) in that previous study were adults, and we have noticed that prevalence of ADHD in our sample is higher in the older age groups. Using the Swedish Patient Register, Cederlöf et al analyzed the association between psychiatric disorders and hypermobility syndrome or EDS (all ages and all 13 subtypes, since they have the same diagnostic code).10 They found that 4.3% of all EDS patients had an ADHD diagnosis, compared to 0.8% in the control group. Siblings of those with EDS also had an increased incidence of ADHD compared to siblings in the control group. In those persons with hypermobility syndrome, 3.0% had ADHD compared to 0.5% in the control group. EDS was associated with ASD (in 2.9% patients vs. 0.4% in comparison individuals), while 1.6% of patients with hypermobility syndrome had ASD compared to 1.2% controls.10 Our study population is not completely comparable to the Cederlöf study population, as their study did not separate the EDS types; moreover, they did not separate age groups. However, our results are in line with Cederlöf regarding the higher presence of ADHD among patients with EDS than those with HSD. We have found that significantly more children with hEDS have been diagnosed with ADHD than children with HSD. In contrast to recently published results of the study, in which ADHD was more common in patients with HSD (although an older sample than ours: mean age 36.1) than in those with EDS.8
More than half of the children with HSD or hEDS had at least one symptom from the gastrointestinal tract; the most common was constipation, which was reported in over two fifths of the cohort. Children with HSD and coexisting ADHD had significantly higher rates of gastritis and reflux, which is in line with previous studies showing an association between ADHD and gastroesophageal reflux disease.25 In our study, more than one in eight children with HSD or hEDS had urinary incontinence, of whom those with ADHD had a significantly higher risk of urinary tract problems. The fact that ADHD is more common in children with overactive bladder than in healthy children is already established.26 The incidence of pain was similar in those with an ADHD diagnosis compared to those without an ADHD diagnosis. Our theory that children with ADHD have an increased sensitivity to pain stimuli was not borne out in our study, nor did treatment with central stimulants result in a reduced frequency of reported pain in the patients’ medical records. Since pain perception is associated with ADHD and methylphenidate administration,27 one would expect differences among groups in our study. However, this was not observed.
Nearly half of the children in our cohort reported sleep problems. The central symptom of fatigue in HSD and hEDS may be associated with sleep problems and coexisting neurodevelopmental disorders. It is known that children with ADHD or ASD are at increased risk of sleep problems.28–30 Our findings confirm that both fatigue and sleep problems are over-represented in children with a diagnosis of ADHD or ASD. Treatment with CNS stimulants may have an effect on sleep in children with ADHD, but the individual variation in drug response and sleep problems is not completely understood.31 The tendency toward fewer sleep problems among the children in our cohort who were being treated for ADHD with CNS stimulants, although not statistically significant, warrants further investigation. Interestingly, we saw that sleep problems were strongly over-represented in the group of children who were undergoing investigation for ADHD. This may imply that it is the ADHD symptoms themselves and not the treatment with CNS stimulants that may affect sleep. Children with ASD are at increased risk of sleep disturbances30 and this was confirmed in our study, where more than 9 in 10 children with ASD had sleep problems.
The degree of hypermobility (according to the Beighton scale) showed no relation to the degree of associated symptoms, which suggests that hypermobility is only a sub-symptom; this has recently been confirmed by McGillis et al.15 Most of the key observed symptoms were somewhat more common in the hEDS
group than the HSD group, although only fatigue and a diagnosis of ADHD were significantly more common; this is what we expected because these are criteria-based diagnoses, and more criteria are required for a hEDS diagnosis than for HSD. However, none of these associated symptoms are included in the hEDS or HSD criteria.19
The strength of our study is the use of data from subjects in a naturalistic, clinical setting with a large clinical sample. Our study points to the importance of actively and systematically asking children and their caregivers about associated symptoms of joint hypermobility-related disorders. Pain from the musculoskeletal system often arises as a topic naturally during the clinic visit, but gastrointestinal symptoms, urinary tract problems and, above all, problems related to sleep and neuropsychiatric symptoms should be actively elicited in the patient history. Our results are dependent on what questions the doctor posed at the time of the examination and whether the answer was recorded. We can thus expect our figures to be somewhat low, compared to systematically asking each patient about all these associated symptoms. In addition, it was not possible to estimate the degree of pain and fatigue through the medical records, as well as the burden of sleep problems. In order to standardize comprehensives of the physician’s visit, the authors of the present study have proposed the standardized manual which is now being applied in clinics at every visit of children with suspected HSD/hEDS.The results obtained in our study derived from a clinical sample at the Department of Pediatrics. In case of suspicion of a neurodevelopmental disorder, children were referred to the Department of Child and Adolescent Psychiatry that, consequently, if they confirmed suspicions as well, performed a diagnostic process according to their own standard diagnostic procedure. However, exploration of the exact diagnostic procedure and diagnostic criteria of neurodevelopmental disorders, that were used, were not part of this study’s scope, which is one of the study’s limitations. Nevertheless, since the study is retrospective and none of the authors were actively involved in the diagnostic process of neurodevelopmental disorders in our cohort, the possibility for influencing the obtained results is unlikely. In clinical practice we have noticed that children with hEDS/HSD have prominent co-occurring symptoms of ADHD and ASD, and thus, in reviewing medical records, we have focused only on these two neurodevelopmental disorders. Since we have not collected data for all disorders in comorbidity, such as neurological, psychiatric or other neurodevelopmental disorders, this is also a clear limitation to our study. Another weakness of the study is that we have a low number of patients with ASD, which causes statistical difficulties.
Go to:
Conclusions
In summary, this study showed an unexpectedly large association between neuropsychiatric symptoms and HSD or hEDS. The frequency of sleep disorders was also unexpectedly high. The results of this study indicate that children with these diagnoses may need to be screened for neuropsychiatric symptoms and preferably also for sleep disorders. There is a great need for further research in this area because, from a clinical point of view, it will help to assure the best possible treatment options according to the etiology. Thus, identifying one biological marker for both ADHD and EDS32 may be one possible direction.Our research group has recently started a prospective study (the BALTHazar study from Swedish „Barn med symtom på ADHD, Ledsmärta och Trötthet vid Hypermobilitet„ or children with symptoms of ADHD, joint pain, fatigue and hypermobility), with targeted investigations for, among other things, ADHD symptoms, ASD, and sleep disorders. If these are found to be a major part of the symptomatology in children with HSD and hEDS, then treatment should be focused on these problems, for example through sleep regulation and ADHD treatment.
Go to:
Funding Statement
This research was funded by Research & Development Centre, Skaraborg Hospital. The sponsor was not involved in any of the stages from study design to submission of the paper for publication.Go to:
Author Contributions
----
some other study
abstract
Considerable interest has arisen concerning the relationship between hereditary connective tissue disorders such as the Ehlers-Danlos syndromes (EDS)/hypermobility spectrum disorders (HSD) and autism, both in terms of their comorbidity as well as co-occurrence within the same families. This paper reviews our current state of knowledge, as well as highlighting unanswered questions concerning this remarkable patient group, which we hope will attract further scientific interest in coming years. In particular, patients themselves are demanding more research into this growing area of interest, although science has been slow to answer that call. Here, we address the overlap between these two spectrum conditions, including neurobehavioral, psychiatric, and neurological commonalities, shared peripheral neuropathies and neuropathologies, and similar autonomic and immune dysregulation. Together, these data highlight the potential relatedness of these two conditions and suggest that EDS/HSD may represent a subtype of autism.Keywords: autism spectrum disorder, Ehlers-Danlos syndrome, hypermobility spectrum disorders, autonomic disorder, mast cell activation syndrome
--
MNK99
Well-Known Member
- Messages
- 5,560
from the site heds vs hsd. eds society.
Myth #1: The Ehlers-Danlos syndromes are ‘just stretchy skin.’
Reality: The Ehlers-Danlos syndromes are a group of hereditary disorders of connective tissue. Connective tissue is found all over the body, in skin, muscles, tendons and ligaments, blood vessels, organs, gums, eyes, and so on.
They are generally characterized by joint hypermobility (joints that move further than normal range), joint instability (subluxation, a partial separation of the articulating surfaces of a joint; and dislocations, a full separation of the surfaces of a joint), scoliosis and other joint deformities, skin hyperextensibility (skin that can be stretched further than normal) and abnormal scarring, and other structural weakness such as hernias and organ prolapse through the pelvic floor. In the rarer types of EDS, there is also a weakness of specific tissues that can lead, for example, to major gum and dental disease, eye disease, cardiac valve and aortic root disorders, and life-threatening abdominal organ, uterine, or blood vessel rupture.
Other problems such as fatigue, headaches, GI problems, and autonomic dysfunction are often seen as part of EDS. These are known as comorbid conditions or associated symptoms and conditions. These add complexity to the presentation of their condition and its management. Such related disorders include, for example, functional bowel disorders, autonomic dysfunction, chronic fatigue, neurological concerns including cord and nerve entrapment and sensory neuropathy, immune hypersensitivity, anxiety disorders, depression, and neurodevelopmental concerns such as ASD and ADHD.
Myth #2: EDS and HSD is ‘just being a bit bendy.’
Reality: Much more than ‘just’ hypermobility, people with EDS and HSD experience joint instability (subluxations and/or dislocations) and reduced position sense (proprioception) with an increased risk of injury to the tissues around joints and the surface of joints.
Hypermobility that does not cause pain or other symptoms is referred to as “asymptomatic joint hypermobility” and does not need to be treated. The problem occurs when joints are not just hypermobile but are also unstable. This results in joint sprains, and/or other injuries, which cause both acute and chronic pain and problems with daily life.
Myth #3: Hypermobile EDS (hEDS) is more severe than hypermobility spectrum disorder (HSD).
Reality: HSD, just like hypermobile Ehlers-Danlos syndrome (hEDS) and rarer types of EDS, can have significant effects on a person’s health, whether this is related to their joints or to comorbidities. Among the most common of these concerns are nausea, vomiting, acid reflux, bloating, pain, absorption, and food intolerance concerns; autonomic disturbances of heart rate and blood pressure, bowel and bladder function, and temperature regulation; anxiety, depression, and phobias; and organ / systemic inflammation related to mast cell activation. These associations are very real. They seriously affect quality of life, and they need to be managed. These additional problems need to be evaluated and treated when an HSD is diagnosed.
Whatever the problems that arise, whatever the diagnosis, it is important that these effects are managed appropriately, and that each person is treated as an individual. HSD and hEDS can be equal in severity, but more importantly, both need similar management, validation, and care.
Myth #4: Hypermobile EDS (hEDS) is diagnosed by genetic testing.
Reality: The genetic variant(s) that causes hEDS has not yet been identified. All other types of EDS have known genetic causes and can be confirmed through genetic testing. A diagnosis of hEDS is made clinically using the 2017 diagnostic criteria. There is no genetic test yet for hEDS.
In some cases of hEDS, a doctor may think it is necessary to run a genetic test to rule out another type of EDS before being satisfied the person has hEDS. This might happen in cases where there are signs or family history, for example, that the doctor thinks could also fit with one of the rarer types of EDS.
The Ehlers-Danlos Society is funding research to find the underlying genetic markers for hEDS. In 2018, the $ 2 million Hypermobile Ehlers Danlos Genetic Evaluation (HEDGE) was launched, a global study to devoted to finding these genetic causes and helping in the search for a diagnostic test. The HEDGE study will recruit, screen, and undertake genetic sequencing tests on 1000 individuals who have been diagnosed with hypermobile EDS by the most recent clinical criteria established in 2017.
In 2021, The Ehlers-Danlos Society awarded $1million to researchers for molecular studies in hEDS and hypermobility spectrum disorders (HSD). A further $260,000 in research funding was awarded in late 2021 to accelerate diagnostic tools. There is currently an unmet clinical need for the development of sensitive and unbiased diagnostic tools for hEDS. Dr. Chip Norris at the Medical University of South Carolina, Principal Investigator, and Dr. Clair Francomano of IU University, Co-Investigator, will lead a newly funded study in collaboration with The Ehlers-Danlos Society Hypermobility Network.
This research study will seek to lead to the development of an accurate and rapid diagnostic test that can be accessible for all individuals living with hEDS, globally, overcoming the many barriers that people with hEDS face in receiving a proper diagnosis.
In 2022, The Ehlers-Danlos Society announced $400,000 towards a new comprehensive study of blood and DNA in individuals with HSD and hEDS. This study, made possible through the generosity of donors, is enrolling fifty people with a diagnosis of hEDS and fifty people with a diagnosis of HSD to examine levels of blood proteins, epigenetic marks on DNA, and DNA sequence. This will be the largest, most comprehensive examination of blood protein levels to date and may provide insights into the nature of the disorders as well as possibly advancing diagnosis and treatment.
Additionally, the study will examine the way DNA is “marked” in people with hEDS and HSD. These chemical (epigenetic) marks on DNA serve as an additional layer of information controlling the expression of genes and could be involved in causing these conditions. This will be the first study of such epigenetic marking of DNA in hEDS or HSD.
Myth #5: There is no treatment for EDS or HSD.
Reality: There are many ways in which the symptoms and complications of EDS and HSD are treated. Often doctors and therapists will use many of the same treatments that are available for other pain disorders, and adapt them e.g., as done in physical therapy.
The same applies to treating associated concerns, though there may be specific causes for the associated symptoms that need to be understood to optimize treatment e.g., slow gut transit, bladder inflammation, sensory neuropathy etc.
Vascular pathologies in EDS need close monitoring, and management to reduce the risk of high blood pressure, potentially need B blocker or ACE inhibitor medication, and may require surgery.
These are just a few examples of the many treatments in EDS and HSD.
Myth #6: EDS and HSD don’t cause pain.
Reality: The most common concerns reported by more than 90% of people presenting to their doctor with EDS or HSD are pain and fatigue.
The pain may be coming from their joints (arthralgia), their muscles (myalgia), a neurological concern (neuralgia) or from organs in the abdomen and pelvis (visceral pain). In addition, studies have also shown that pain experienced during bleeding in the period cycle (menorrhagia) is greater in some people with EDS than in the general population.
There are many reasons why someone with EDS or HSD might have pain.
Myth #8: EDS and HSD can be treated with collagen supplements.
Reality: There is no evidence that collagen supplements help people who have EDS or HSD. The collagen in the supplement is broken down during digestion like all other proteins and does not help repair or replace the faulty collagen produced by the body.
Most types of EDS cause defective collagen, not a collagen deficiency. No supplement changes the genetic “directions” to keep producing defective collagen.
Myth #9: You can be ‘too old’ or ‘too young’ to have EDS or HSD.
Reality: EDS and HSD affect people of all ages. People are born with these conditions and are affected by them throughout their lives. Symptoms may be apparent from birth, begin at puberty, or become apparent later in life.
Myth #10: ‘You don’t look like someone who has EDS or HSD.’
Reality: People from all races, genders, ages, and body shapes can have EDS or HSD. In the rarer types of EDS, there may be characteristic facial features, but this is not true all of the time. Otherwise, there isn’t a known ‘look’ in EDS or HSD so the comment ‘you don’t look like someone with hEDS or HSD'.
Myth #1: The Ehlers-Danlos syndromes are ‘just stretchy skin.’
Reality: The Ehlers-Danlos syndromes are a group of hereditary disorders of connective tissue. Connective tissue is found all over the body, in skin, muscles, tendons and ligaments, blood vessels, organs, gums, eyes, and so on.
They are generally characterized by joint hypermobility (joints that move further than normal range), joint instability (subluxation, a partial separation of the articulating surfaces of a joint; and dislocations, a full separation of the surfaces of a joint), scoliosis and other joint deformities, skin hyperextensibility (skin that can be stretched further than normal) and abnormal scarring, and other structural weakness such as hernias and organ prolapse through the pelvic floor. In the rarer types of EDS, there is also a weakness of specific tissues that can lead, for example, to major gum and dental disease, eye disease, cardiac valve and aortic root disorders, and life-threatening abdominal organ, uterine, or blood vessel rupture.
Other problems such as fatigue, headaches, GI problems, and autonomic dysfunction are often seen as part of EDS. These are known as comorbid conditions or associated symptoms and conditions. These add complexity to the presentation of their condition and its management. Such related disorders include, for example, functional bowel disorders, autonomic dysfunction, chronic fatigue, neurological concerns including cord and nerve entrapment and sensory neuropathy, immune hypersensitivity, anxiety disorders, depression, and neurodevelopmental concerns such as ASD and ADHD.
Myth #2: EDS and HSD is ‘just being a bit bendy.’
Reality: Much more than ‘just’ hypermobility, people with EDS and HSD experience joint instability (subluxations and/or dislocations) and reduced position sense (proprioception) with an increased risk of injury to the tissues around joints and the surface of joints.
Hypermobility that does not cause pain or other symptoms is referred to as “asymptomatic joint hypermobility” and does not need to be treated. The problem occurs when joints are not just hypermobile but are also unstable. This results in joint sprains, and/or other injuries, which cause both acute and chronic pain and problems with daily life.
Myth #3: Hypermobile EDS (hEDS) is more severe than hypermobility spectrum disorder (HSD).
Reality: HSD, just like hypermobile Ehlers-Danlos syndrome (hEDS) and rarer types of EDS, can have significant effects on a person’s health, whether this is related to their joints or to comorbidities. Among the most common of these concerns are nausea, vomiting, acid reflux, bloating, pain, absorption, and food intolerance concerns; autonomic disturbances of heart rate and blood pressure, bowel and bladder function, and temperature regulation; anxiety, depression, and phobias; and organ / systemic inflammation related to mast cell activation. These associations are very real. They seriously affect quality of life, and they need to be managed. These additional problems need to be evaluated and treated when an HSD is diagnosed.
Whatever the problems that arise, whatever the diagnosis, it is important that these effects are managed appropriately, and that each person is treated as an individual. HSD and hEDS can be equal in severity, but more importantly, both need similar management, validation, and care.
Myth #4: Hypermobile EDS (hEDS) is diagnosed by genetic testing.
Reality: The genetic variant(s) that causes hEDS has not yet been identified. All other types of EDS have known genetic causes and can be confirmed through genetic testing. A diagnosis of hEDS is made clinically using the 2017 diagnostic criteria. There is no genetic test yet for hEDS.
In some cases of hEDS, a doctor may think it is necessary to run a genetic test to rule out another type of EDS before being satisfied the person has hEDS. This might happen in cases where there are signs or family history, for example, that the doctor thinks could also fit with one of the rarer types of EDS.
The Ehlers-Danlos Society is funding research to find the underlying genetic markers for hEDS. In 2018, the $ 2 million Hypermobile Ehlers Danlos Genetic Evaluation (HEDGE) was launched, a global study to devoted to finding these genetic causes and helping in the search for a diagnostic test. The HEDGE study will recruit, screen, and undertake genetic sequencing tests on 1000 individuals who have been diagnosed with hypermobile EDS by the most recent clinical criteria established in 2017.
In 2021, The Ehlers-Danlos Society awarded $1million to researchers for molecular studies in hEDS and hypermobility spectrum disorders (HSD). A further $260,000 in research funding was awarded in late 2021 to accelerate diagnostic tools. There is currently an unmet clinical need for the development of sensitive and unbiased diagnostic tools for hEDS. Dr. Chip Norris at the Medical University of South Carolina, Principal Investigator, and Dr. Clair Francomano of IU University, Co-Investigator, will lead a newly funded study in collaboration with The Ehlers-Danlos Society Hypermobility Network.
This research study will seek to lead to the development of an accurate and rapid diagnostic test that can be accessible for all individuals living with hEDS, globally, overcoming the many barriers that people with hEDS face in receiving a proper diagnosis.
In 2022, The Ehlers-Danlos Society announced $400,000 towards a new comprehensive study of blood and DNA in individuals with HSD and hEDS. This study, made possible through the generosity of donors, is enrolling fifty people with a diagnosis of hEDS and fifty people with a diagnosis of HSD to examine levels of blood proteins, epigenetic marks on DNA, and DNA sequence. This will be the largest, most comprehensive examination of blood protein levels to date and may provide insights into the nature of the disorders as well as possibly advancing diagnosis and treatment.
Additionally, the study will examine the way DNA is “marked” in people with hEDS and HSD. These chemical (epigenetic) marks on DNA serve as an additional layer of information controlling the expression of genes and could be involved in causing these conditions. This will be the first study of such epigenetic marking of DNA in hEDS or HSD.
Myth #5: There is no treatment for EDS or HSD.
Reality: There are many ways in which the symptoms and complications of EDS and HSD are treated. Often doctors and therapists will use many of the same treatments that are available for other pain disorders, and adapt them e.g., as done in physical therapy.
The same applies to treating associated concerns, though there may be specific causes for the associated symptoms that need to be understood to optimize treatment e.g., slow gut transit, bladder inflammation, sensory neuropathy etc.
Vascular pathologies in EDS need close monitoring, and management to reduce the risk of high blood pressure, potentially need B blocker or ACE inhibitor medication, and may require surgery.
These are just a few examples of the many treatments in EDS and HSD.
Myth #6: EDS and HSD don’t cause pain.
Reality: The most common concerns reported by more than 90% of people presenting to their doctor with EDS or HSD are pain and fatigue.
The pain may be coming from their joints (arthralgia), their muscles (myalgia), a neurological concern (neuralgia) or from organs in the abdomen and pelvis (visceral pain). In addition, studies have also shown that pain experienced during bleeding in the period cycle (menorrhagia) is greater in some people with EDS than in the general population.
There are many reasons why someone with EDS or HSD might have pain.
Myth #8: EDS and HSD can be treated with collagen supplements.
Reality: There is no evidence that collagen supplements help people who have EDS or HSD. The collagen in the supplement is broken down during digestion like all other proteins and does not help repair or replace the faulty collagen produced by the body.
Most types of EDS cause defective collagen, not a collagen deficiency. No supplement changes the genetic “directions” to keep producing defective collagen.
Myth #9: You can be ‘too old’ or ‘too young’ to have EDS or HSD.
Reality: EDS and HSD affect people of all ages. People are born with these conditions and are affected by them throughout their lives. Symptoms may be apparent from birth, begin at puberty, or become apparent later in life.
Myth #10: ‘You don’t look like someone who has EDS or HSD.’
Reality: People from all races, genders, ages, and body shapes can have EDS or HSD. In the rarer types of EDS, there may be characteristic facial features, but this is not true all of the time. Otherwise, there isn’t a known ‘look’ in EDS or HSD so the comment ‘you don’t look like someone with hEDS or HSD'.
MNK99
Well-Known Member
- Messages
- 5,560
Stims..mg.. meat.. diet and strength training helped me at 22 and 23... and dex 26 on .
and sarms at 27 (tho ya u can get suppressed, shutdown forever), helped the spinal and lifting parts of hEDS/HSD, letting me be jacked and workout as often as I wanted to again, like at 23 and at 18 again but way stronger. I was pretty strong at 23-25 also but working out 4-5x was getting hard per week. Most of late 20s and beyond it was daily or near it. 6d a week. Tho ya i need to get back on track there.
This lady gave her complications/story with PFS from minoxidil or similar. AND also was on propeciahelp and some other sites.
I left warnings on inspire/ eds forum. for minox, fin etc.
anyways i am way past all this shyt.
If i wanna take test ill take it. i am sure knee, ankle, tendons/ligaments pain is less and ill feel better working out but.., i mean 4-5mo doing hard working out and walking, I will do well too.
With just carnivore.
Test cream is nothing to fear tho. Not sure how that would crash and make someone's recovery from PFS go away, or make them way sicker.
I get that it will suppress hormones but I think it is bs.. and just waiting for things to be perfect, when you have to live now isn't worth it.
Some mustard, some hot sauce 4x a mo and staying on carnivore that mo, and 20 cups of coffee vs giving up after 7-8days, for sure the former is better.
"Don't let perfect be the enemy of good."
------------------------------------------------------------------------
I feel bad for this woman but I fixed this and all before... so ppl can recover but ya i find it insane that ppl with marfans and eds that they know about are taking the worst drugs there are, like duta, minox... but yeah most people call em "safe", including their docs and the drug companies, the algos on google, etc, etc. The podcast commercials, everything.
Go to eds
r/eds•10 mo. ago
Fiercebully9
:*** I am far too tired to edit this for the subreddit*** it reads this way because it's copied and pasted from go fund me. I didn't come here to tell people eds exists- but the rest of the world needs the preface **** please do not waste time responding to the way it's addressed. It was not written to address people with eds. I'm posting it so that people know the risk of taking the things I did. I had very mild heds before this happened. I wish every second I could go back in time. I'll never be able to go in the sun again or use a washcloth.
Hi everyone,
My name is Celia. I believe I am one of many people experiencing extreme and irreversible side effects of a common hair loss medication known as minoxidil. I also believe that the impact on my health has been more severe due to a deficit in research on connective tissue disorders like Ehlers Danlos Syndrome, a condition most commonly found in women.
My hope is to direct money and attention to this issue and motivate further research on the topic in order to 1) ensure no-one else finds themselves the unknowing victim of these side-effects, and 2) to chart a medical path forward.
I began taking minoxidil for stress-related hair loss associated with a tethered spinal cord (for which I had surgery), and the exhaustion of navigating the healthcare system with what I now understand to be the poorly understood connective tissue disorder, Ehlers Danlos Syndrome.:
and sarms at 27 (tho ya u can get suppressed, shutdown forever), helped the spinal and lifting parts of hEDS/HSD, letting me be jacked and workout as often as I wanted to again, like at 23 and at 18 again but way stronger. I was pretty strong at 23-25 also but working out 4-5x was getting hard per week. Most of late 20s and beyond it was daily or near it. 6d a week. Tho ya i need to get back on track there.
This lady gave her complications/story with PFS from minoxidil or similar. AND also was on propeciahelp and some other sites.
I left warnings on inspire/ eds forum. for minox, fin etc.
anyways i am way past all this shyt.
If i wanna take test ill take it. i am sure knee, ankle, tendons/ligaments pain is less and ill feel better working out but.., i mean 4-5mo doing hard working out and walking, I will do well too.
With just carnivore.
Test cream is nothing to fear tho. Not sure how that would crash and make someone's recovery from PFS go away, or make them way sicker.
I get that it will suppress hormones but I think it is bs.. and just waiting for things to be perfect, when you have to live now isn't worth it.
Some mustard, some hot sauce 4x a mo and staying on carnivore that mo, and 20 cups of coffee vs giving up after 7-8days, for sure the former is better.
"Don't let perfect be the enemy of good."
------------------------------------------------------------------------
I feel bad for this woman but I fixed this and all before... so ppl can recover but ya i find it insane that ppl with marfans and eds that they know about are taking the worst drugs there are, like duta, minox... but yeah most people call em "safe", including their docs and the drug companies, the algos on google, etc, etc. The podcast commercials, everything.
Go to eds
r/eds•10 mo. ago
Fiercebully9
IMPORTANT ** life threatening medication harm for those with Eds
Adverse Drug Reactions:*** I am far too tired to edit this for the subreddit*** it reads this way because it's copied and pasted from go fund me. I didn't come here to tell people eds exists- but the rest of the world needs the preface **** please do not waste time responding to the way it's addressed. It was not written to address people with eds. I'm posting it so that people know the risk of taking the things I did. I had very mild heds before this happened. I wish every second I could go back in time. I'll never be able to go in the sun again or use a washcloth.
Hi everyone,
My name is Celia. I believe I am one of many people experiencing extreme and irreversible side effects of a common hair loss medication known as minoxidil. I also believe that the impact on my health has been more severe due to a deficit in research on connective tissue disorders like Ehlers Danlos Syndrome, a condition most commonly found in women.
My hope is to direct money and attention to this issue and motivate further research on the topic in order to 1) ensure no-one else finds themselves the unknowing victim of these side-effects, and 2) to chart a medical path forward.
I began taking minoxidil for stress-related hair loss associated with a tethered spinal cord (for which I had surgery), and the exhaustion of navigating the healthcare system with what I now understand to be the poorly understood connective tissue disorder, Ehlers Danlos Syndrome.:
MNK99
Well-Known Member
- Messages
- 5,560
I know my body and my mind... and that food is depleted.
I'd be fine eating a tiny bit earlier.., in day, and also with only one meal a day.
OR even whey then carnivore and no supps but that is complicated and hard to only keep those up... unless it is beef only protein. no dextrose lactose etc.
Anyways... b1, b2, mg... enzymes hcl optional (those 2), and a chelator and carnivore and dex... and test id be fine.
u need mg with EDS. there are like 40 page papers on it. Probaby b also. IF u get it all from diet that's one thing
but also steroids like test, and also stimulants like dex, literally deplete mg, b1 maybe, b2 maybe. and also adding b6 should help autism.
but yeah i will do tei later.
maybe i can get all from diet but most people cannot.
i don't do random shyt, only things that make a lot of sense.
WHAT WAS I DOING on sarms... and mg, dex before that and just coke mg yrs before that?? treating anxiety, adhd and hEDS. same with tape.
after PFS and hackstasis? later, after tei...?
Just mg b enzymes hcl i was treating hEDS/HSD and helping ADHD (with ADHD medicine). And working out, also helping anxiety, keep depression away, and ADHD.
I just needed some further help... MDMA and the like and maybe TEI.
I really don't think TEI is curing everyone's spine etc. BUT I will give it a try for autism, depression, anxiety (I can cure those two latter ones for sure). Curing all of ASD and ADHD sounds like fixing my spine, sounds like pseudoscience and bs but I don't know. Same with carnivore, it can help all those too.
SOME test cream never hurt anyone... people did designer steroids and 20 androgens for this shyt... i am doing test cream to up dht.. years after randro / 4andro.
if i waste 5-10d of medicine and dont take it straight that sucks tho, but i can get more in a phonecall but ya u want to take it straight/ solidly. i am indecisive.
i will take it if i feel it helps. maybe lift 3-4 sets without and try it a few days see if it helps.. joint instability. i am sure it does and i am sure i've had very bad joint instability before, hence all the injuries going back 20-25 yrs, and not lifting right now. Plus I want carniv to kick in harder.
I'd be fine eating a tiny bit earlier.., in day, and also with only one meal a day.
OR even whey then carnivore and no supps but that is complicated and hard to only keep those up... unless it is beef only protein. no dextrose lactose etc.
Anyways... b1, b2, mg... enzymes hcl optional (those 2), and a chelator and carnivore and dex... and test id be fine.
u need mg with EDS. there are like 40 page papers on it. Probaby b also. IF u get it all from diet that's one thing
but also steroids like test, and also stimulants like dex, literally deplete mg, b1 maybe, b2 maybe. and also adding b6 should help autism.
but yeah i will do tei later.
maybe i can get all from diet but most people cannot.
i don't do random shyt, only things that make a lot of sense.
WHAT WAS I DOING on sarms... and mg, dex before that and just coke mg yrs before that?? treating anxiety, adhd and hEDS. same with tape.
after PFS and hackstasis? later, after tei...?
Just mg b enzymes hcl i was treating hEDS/HSD and helping ADHD (with ADHD medicine). And working out, also helping anxiety, keep depression away, and ADHD.
I just needed some further help... MDMA and the like and maybe TEI.
I really don't think TEI is curing everyone's spine etc. BUT I will give it a try for autism, depression, anxiety (I can cure those two latter ones for sure). Curing all of ASD and ADHD sounds like fixing my spine, sounds like pseudoscience and bs but I don't know. Same with carnivore, it can help all those too.
SOME test cream never hurt anyone... people did designer steroids and 20 androgens for this shyt... i am doing test cream to up dht.. years after randro / 4andro.
if i waste 5-10d of medicine and dont take it straight that sucks tho, but i can get more in a phonecall but ya u want to take it straight/ solidly. i am indecisive.
i will take it if i feel it helps. maybe lift 3-4 sets without and try it a few days see if it helps.. joint instability. i am sure it does and i am sure i've had very bad joint instability before, hence all the injuries going back 20-25 yrs, and not lifting right now. Plus I want carniv to kick in harder.
MNK99
Well-Known Member
- Messages
- 5,560
Stupid list but sure 18-19 or so of these. I said the ADHD test was stupid too and got 17/18 with my first and well liked ADHD specialist (he is a P.doc). He said the last q was for children. It was about climbing furniture. Yeah still do that tbh,
Connective tissues are made up of proteins and other substances that provide them with elasticity.
In people with Ehler-Danlos syndrome, the strength of collagen is affected.
Though people with Ehler-Danlos syndrome are born with the condition, it may take years before it gets diagnosed.
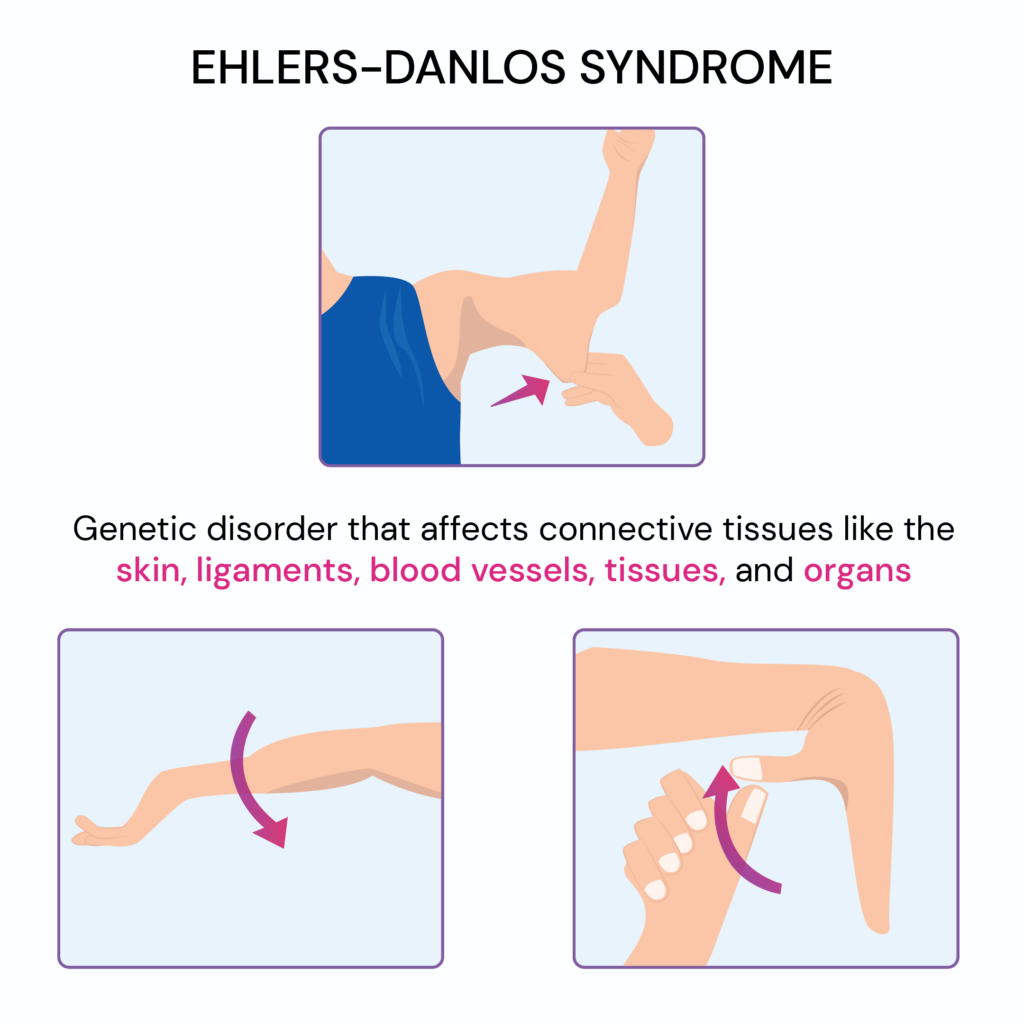
Hypermobile EDS (hEDS) is the most common type of Ehler-Danlos syndrome.
Some symptoms of hEDS are:
Usually, the diagnosis is based on the individual’s history, symptoms, and physical examination.
Other relatively common types of EDS are classical, vascular, and kyphoscoliotic EDS.
A few genes that have been associated with Ehler-Danlos syndrome are:
Changes (variants) in these genes may disrupt the production or processing of collagen, resulting in weak bones, skin, or other parts of the body.
This gives rise to the characteristic features of Ehler-Danlos syndrome.
Each type of EDS is caused by variants in different collagen genes.
While for some, it may be related to an underlying medical condition, these may be signs of Ehler-Danlos syndrome for a few people.
23 signs of of Ehler-Danlos Syndrome
Treatment is aimed at managing the symptoms and preventing further complications.
A few ways to manage Ehler-Danlos syndrome are:
People with Ehler-Danlos syndrome have fragile blood vessels. So, doctors may want to lower their blood pressure with medications.
The healthcare team for EDS usually includes an occupational therapist, physiotherapist, and counselors.
Genetic counseling may help people understand their condition, how it is inherited, and the risk of passing it to their children.
There’s no specific treatment for EDS, but it’s possible to manage many of the symptoms.
What Is Ehlers-Danlos Syndrome?
Ehler-Danlos syndrome is a group of rare inherited disorders that affect the body’s connective tissues, especially the skin, joints, and blood vessels.Connective tissues are made up of proteins and other substances that provide them with elasticity.
In people with Ehler-Danlos syndrome, the strength of collagen is affected.
Though people with Ehler-Danlos syndrome are born with the condition, it may take years before it gets diagnosed.
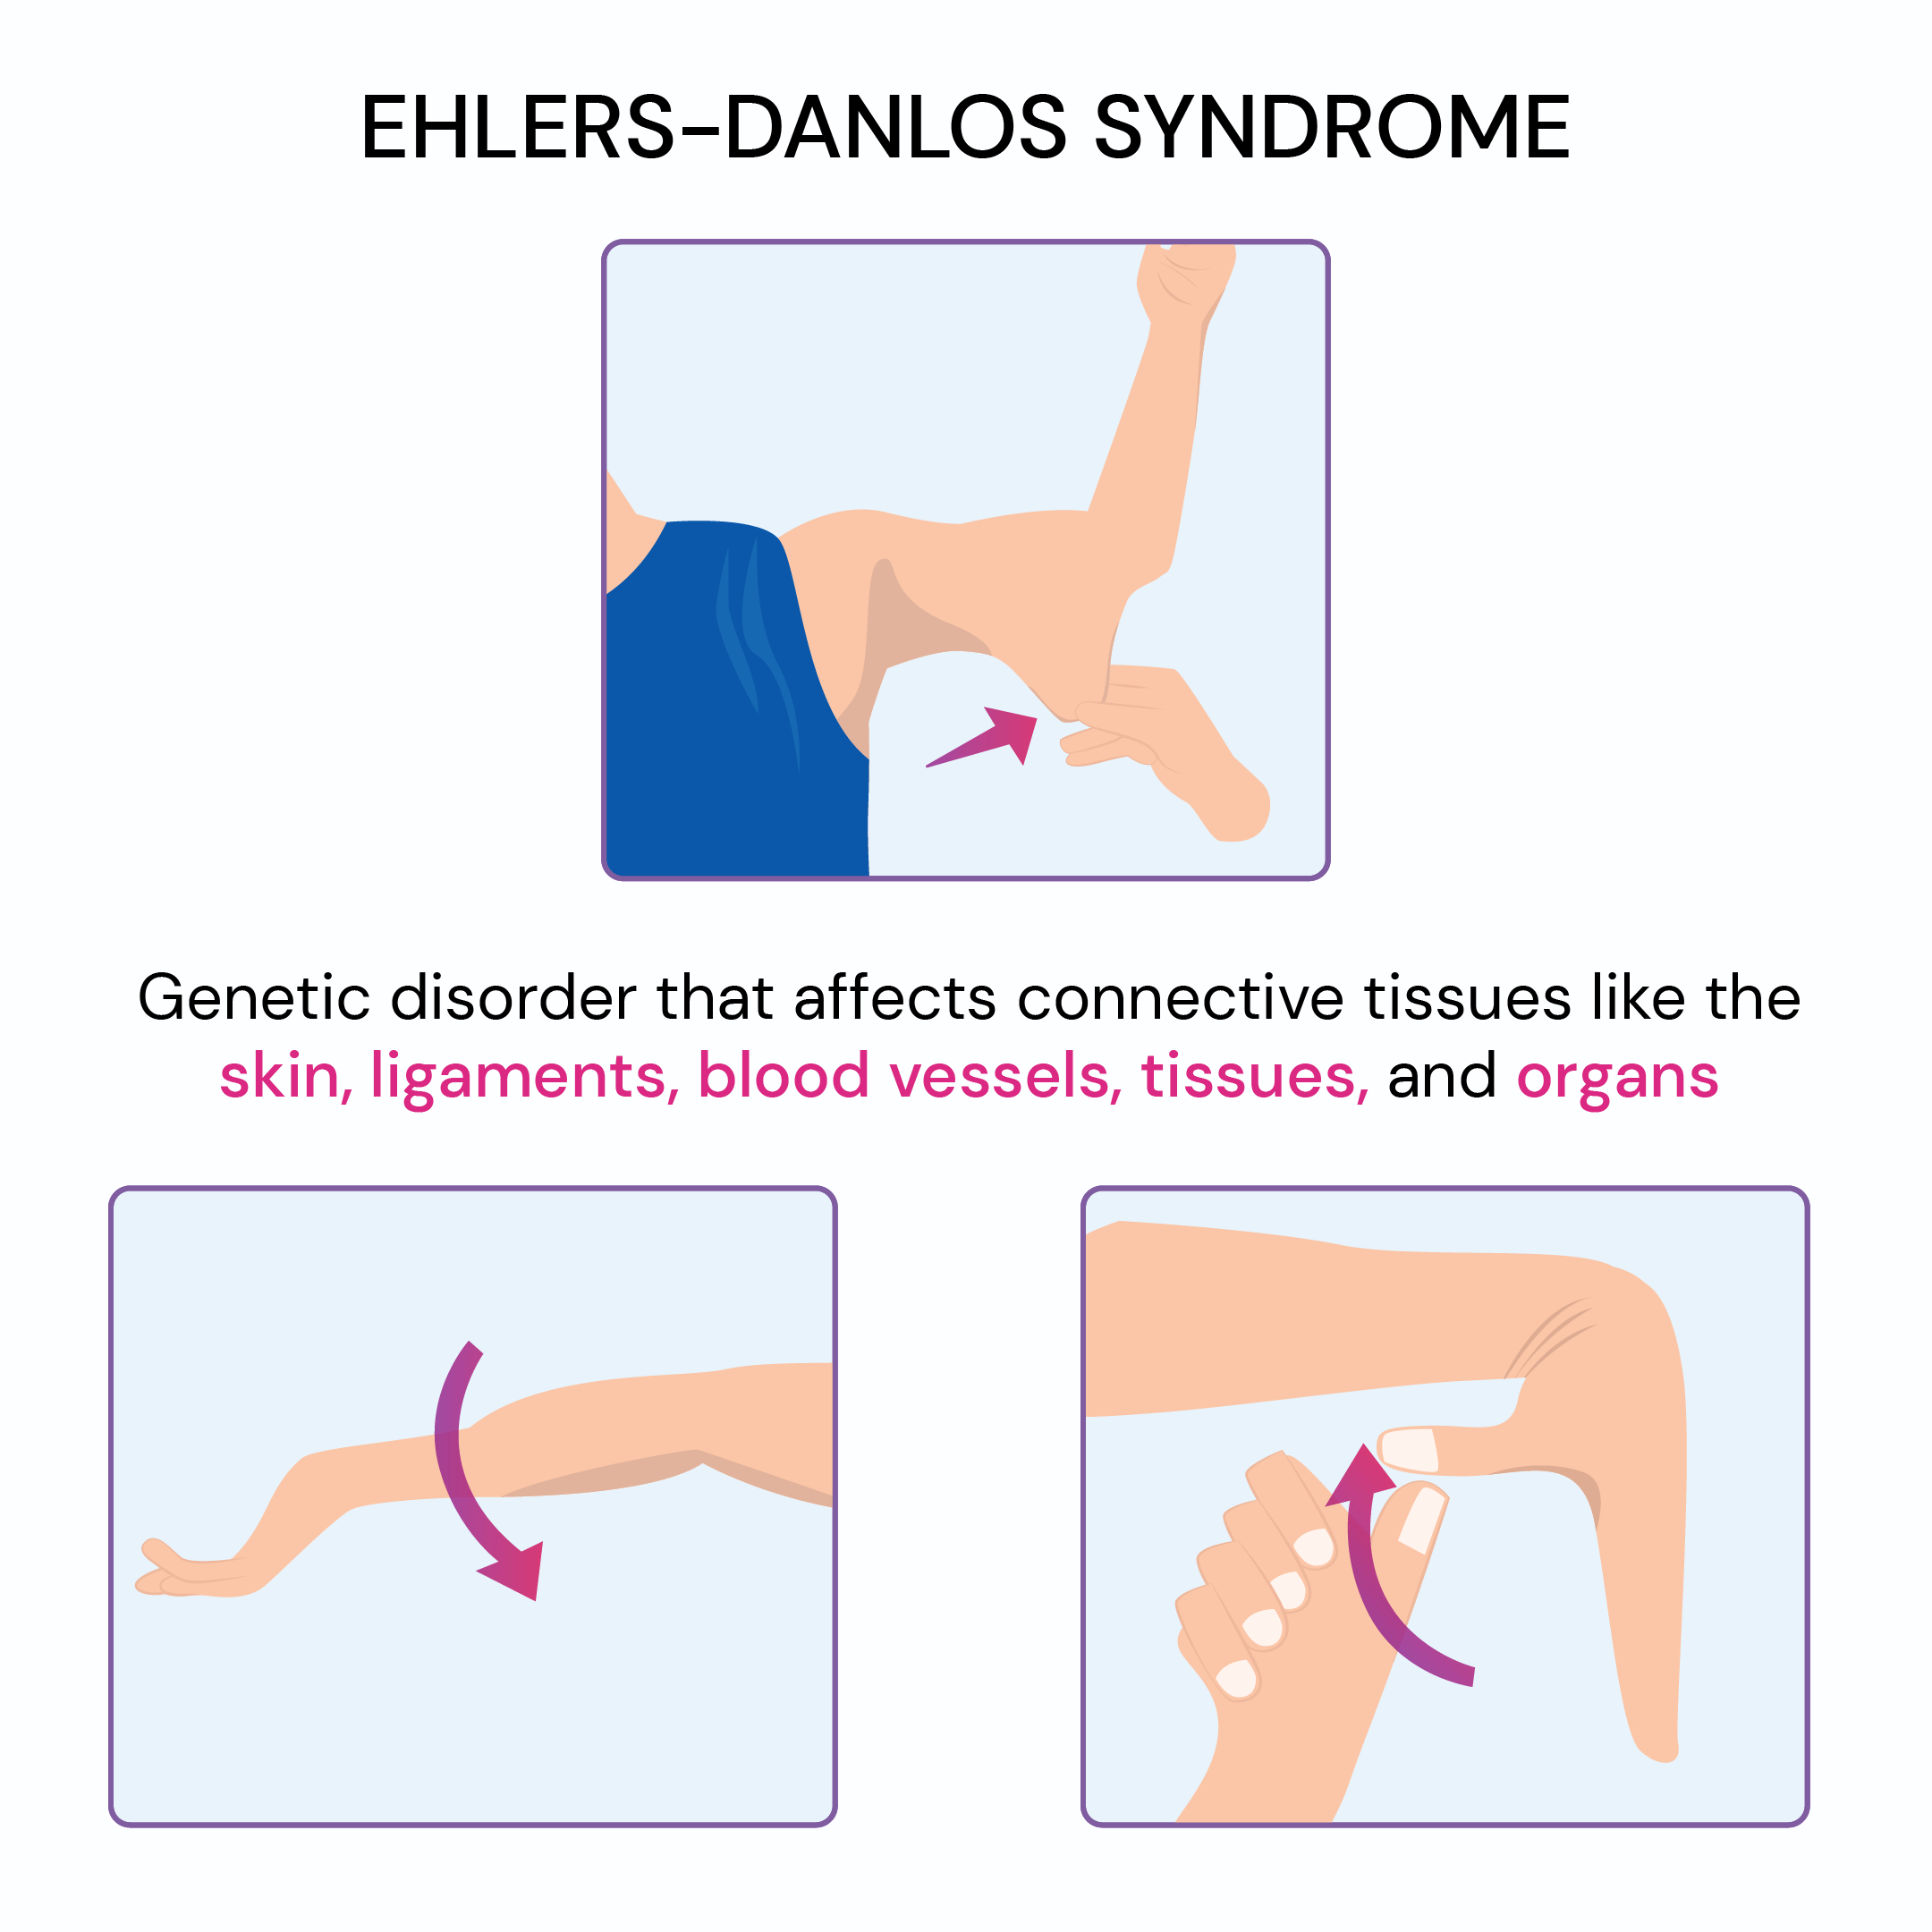
Types of Ehlers-Danlos Syndrome
There are 13 types of Ehler-Danlos syndromes (EDS), most of which are rare.Hypermobile EDS (hEDS) is the most common type of Ehler-Danlos syndrome.
Some symptoms of hEDS are:
- Hypermobility of joints
- Unstable joints that tend to dislocate easily
- Clicking and pain in the joints
- Easy skin bruising
- Digestive problems like heartburn
- Dizziness and increased heart rate after standing up
- Urinary incontinence
Usually, the diagnosis is based on the individual’s history, symptoms, and physical examination.
Other relatively common types of EDS are classical, vascular, and kyphoscoliotic EDS.
Is Elhers-Danlos Syndrome Genetic?
Ehler-Danlos syndrome is a genetic condition. Over 20 genes have been found to be associated with EDS.A few genes that have been associated with Ehler-Danlos syndrome are:
- COL1A1
- COL1A2
- COL3A1
- COL5A2
Changes (variants) in these genes may disrupt the production or processing of collagen, resulting in weak bones, skin, or other parts of the body.
This gives rise to the characteristic features of Ehler-Danlos syndrome.
Each type of EDS is caused by variants in different collagen genes.
- Variants in the COL5A1, COL5A2, and sometimes in the COL1A1 genes cause the classical type EDS
- Variants in the TNXB gene cause the classical EDS and a few cases of hypermobile type
- Variants in the COL1A2 gene cause cardiovascular EDS and some cases of arthrochalasia
23 Signs You Grew Up With Ehlers-danlos Syndrome
Hypermobile joints, frequent bruising, and painful joints are common symptoms of EDS.While for some, it may be related to an underlying medical condition, these may be signs of Ehler-Danlos syndrome for a few people.
23 signs of of Ehler-Danlos Syndrome
- High flexibility of joints
- Clumsiness
- Frequent tripping or falling
- Frequent joint dislocations, especially of the knee or elbow
- Ability to bend fingers or thumb backward
- Increased frequency of fracturing bones
- Hyperextended knees
- Feeling you are double-jointed
- Fear of relaxing your joints for fear of dislocation
- Frequent dizzy or fainting spells
- Fewer wrinkles
- Frequent foot problems, especially pain and discomfort
- Digestive issues like bloating, diarrhea, nausea, acid reflux
- Extreme fatigue
- Holding a pen or pencil differently to avoid pain, discomfort, or dislocation of your finger joint
- Take longer to complete everyday activities
- Increased likelihood of migraine, vision issues, or postural orthostatic tachycardia syndrome (POTS)
- Chronic body pain at a young age
- Running with a different gait than others
- Picky about the clothing you wear to protect your sensitive skin
- Joints make a clicking or popping noise
- Growing pain in the ankles
- Inability to run fast
Treatment for Ehlers-Danlos Syndromes
There is no cure for Ehler-Danlos syndrome.Treatment is aimed at managing the symptoms and preventing further complications.
A few ways to manage Ehler-Danlos syndrome are:
- Medications: Over-the-counter pain-relieving medications are usually the mainstay for EDS treatment.
People with Ehler-Danlos syndrome have fragile blood vessels. So, doctors may want to lower their blood pressure with medications.
- Physical therapy: Joints with weak connective tissue in Enhler Danlos increases the risk for dislocations.
- Surgery: Surgery may be required in people with repeated joint dislocations or ruptured blood vessels and organs.
The healthcare team for EDS usually includes an occupational therapist, physiotherapist, and counselors.
Genetic counseling may help people understand their condition, how it is inherited, and the risk of passing it to their children.
There’s no specific treatment for EDS, but it’s possible to manage many of the symptoms.
Summary: 23 Signs You Grew Up With Ehlers-Danlos Syndrome
- Ehler-Danlos syndrome (EDS) is a group of rare inherited disorders that affect the body’s connective tissues.
- People with Ehler-Danlos syndrome are born with it, but their symptoms may take years or, sometimes, decades to show.
- There are around 13 different types of Ehler-Danlos syndrome, and hypermobility EDS (hEDS) is the most common type.
- Ehler-Danlos syndrome is a genetic condition; to date, over 20 genes, including COL1A1 and COL1A2, have been associated with the condition.
- Most people with Ehler-Danlos are unaware of their condition as they are unable to spot signs like easy skin bruising and joint dislocation.
MNK99
Well-Known Member
- Messages
- 5,560
I worked really hard to be fitter than 98 99% of people most the time. AND I can work 3x less hard to be fitter than 95% of ppl with a tiny bit of gear. SAME with carnivore only probably (BUT I mean the discipline, years of working out, strict diets, then carnivore... you are still outworking people, just using less effort and a smarter approach).
WOMEN who can't workout take test and can again (with any array of conditions, perimenopause, menopause, HEDS, EDS, arthritits, etc etc).
FROM reddit as a reminder. Anyways my face and hair are good and my skin and mental health is near perfect when i workout lots... i am not gonna workout lots getting 85 90% gains when i can get 95 99% gains and prevent injury.
DOCS and ppl don't want u to use steroids etc, hcg, etc.. bc they actually work. hence, stigmatized. same with carnivore diet, fasting, doing your own research. and being your own doctor.
the who, and the 4 meat processing plants in the USA (3 soon), and kellogs, and coca cola, and pfizer, etc don't care about you.
blah blah blah ya it helps.
any drug that helps and affects how u look positively and helps u psychologically is merely coincidental and they'd get rid of it or restrict it if they could.
soon, more drugs will be out and ai.. and theyll send it to your house. canada and uk etc wont make it badly criminal to have anabolics.. and stims/ to sell em sure. or produce em.
anyways.
r/ ehlers
Anyone on testosterone finding relief from any aspect of EDS?
It’s something I had wondered about in passing, but I just had an eye exam with a doctor who has a lot of EDS patients and they mentioned some people found unexpected benefits from taking testosterone when it came to EDS.
Does anyone have any personal experience with this?
Archived post. New comments cannot be posted and votes cannot be cast
rickEDScricket
hEDS
Yes! I inject low doses of testosterone two times per week. I noticed a big difference mostly in fatigue and and brain fog, but my joint pain has also improved a bit. I recommend talking to your doctor about it
WOMEN who can't workout take test and can again (with any array of conditions, perimenopause, menopause, HEDS, EDS, arthritits, etc etc).
FROM reddit as a reminder. Anyways my face and hair are good and my skin and mental health is near perfect when i workout lots... i am not gonna workout lots getting 85 90% gains when i can get 95 99% gains and prevent injury.
DOCS and ppl don't want u to use steroids etc, hcg, etc.. bc they actually work. hence, stigmatized. same with carnivore diet, fasting, doing your own research. and being your own doctor.
the who, and the 4 meat processing plants in the USA (3 soon), and kellogs, and coca cola, and pfizer, etc don't care about you.
blah blah blah ya it helps.
any drug that helps and affects how u look positively and helps u psychologically is merely coincidental and they'd get rid of it or restrict it if they could.
soon, more drugs will be out and ai.. and theyll send it to your house. canada and uk etc wont make it badly criminal to have anabolics.. and stims/ to sell em sure. or produce em.
anyways.
r/ ehlers
Anyone on testosterone finding relief from any aspect of EDS?
It’s something I had wondered about in passing, but I just had an eye exam with a doctor who has a lot of EDS patients and they mentioned some people found unexpected benefits from taking testosterone when it came to EDS.
Does anyone have any personal experience with this?
Archived post. New comments cannot be posted and votes cannot be cast
rickEDScricket
hEDS
Yes! I inject low doses of testosterone two times per week. I noticed a big difference mostly in fatigue and and brain fog, but my joint pain has also improved a bit. I recommend talking to your doctor about it
MNK99
Well-Known Member
- Messages
- 5,560
--someone:
cEDS, MCAS, POTS, ME, endometriosis, post-oophorectomy
I became functionally allergic to my estrogen because of MCAS and had to get my ovaries removed. I understand that's not as uncommon as it should be. The inflammation caused by the estrogen allergy effectively recreated endometriosis.
And estrogen creates a lot of joint laxity, so it wouldn't surprise me at all. I remember the first few days after my oophorectomy I had so many fewer dislocations that it really shocked me, but I was put on androgen, estrogen and progesterone add-back HRT after about a week and they started up again. Now I'm just on progesterone daily and I do estrogen when I can tolerate it (maybe 1mg every week), just to try to not fall too badly into the osteoporosis hole.
My experience has been as follows:
Joints are much tighter and I have a lot less pain and instability. Downside of this is that I no longer meet Beighton criterion on the hEDS list & that restricts my access to care.
POTS seems to have gotten worse, but it's hard to tell if that's because of T or lifestyle factors which changed around the same time.
I get splitting headaches if I'm late on my T shot.
Not sure if you're trans or not, but T has effects in that area. If you're not comfortable with masculinizing effects, you may be able to take a very low dose, or take a DHT blocker, which restricts certain androgenic effects. Pls talk to an endocrinologist for more detail.
I have MCAS and endometriosis too and I definitely noticed problems with MCAS flares around my period.
I’m a female and my hormones are completely out of whack. I’m not sure if it’s from EDS, having four kids, or being almost 40… At any rate I actually do take a small dose of testosterone weekly and progesterone every night before bed and it actually helps a ton! I’m able to do light workouts again and start working on getting some strength back!
OP
How did you figure out you need it or should try it?
-someone:
I had a bunch of blood tests done including a hormone panel. My testosterone and progesterone both came back at 0.
pre transition (I take estrogen) I had significantly less muscular pain after using my muscles
cavinscabin
hEDS
Yes, absolutely, without a doubt. I've been on T for 2 years now and my pain has definitely decreased since I started
cEDS, MCAS, POTS, ME, endometriosis, post-oophorectomy
I became functionally allergic to my estrogen because of MCAS and had to get my ovaries removed. I understand that's not as uncommon as it should be.
The inflammation caused by the estrogen allergy effectively recreated endometriosis.And estrogen creates a lot of joint laxity, so it wouldn't surprise me at all. I remember the first few days after my oophorectomy I had so many fewer dislocations that it really shocked me, but I was put on androgen, estrogen and progesterone add-back HRT after about a week and they started up again. Now I'm just on progesterone daily and I do estrogen when I can tolerate it (maybe 1mg every week), just to try to not fall too badly into the osteoporosis hole.
My experience has been as follows:
Joints are much tighter and I have a lot less pain and instability. Downside of this is that I no longer meet Beighton criterion on the hEDS list & that restricts my access to care.
POTS seems to have gotten worse, but it's hard to tell if that's because of T or lifestyle factors which changed around the same time.
I get splitting headaches if I'm late on my T shot.
Not sure if you're trans or not, but T has effects in that area. If you're not comfortable with masculinizing effects, you may be able to take a very low dose, or take a DHT blocker, which restricts certain androgenic effects. Pls talk to an endocrinologist for more detail.
I have MCAS and endometriosis too and I definitely noticed problems with MCAS flares around my period.
I’m a female and my hormones are completely out of whack. I’m not sure if it’s from EDS, having four kids, or being almost 40… At any rate I actually do take a small dose of testosterone weekly and progesterone every night before bed and it actually helps a ton! I’m able to do light workouts again and start working on getting some strength back!
OP
How did you figure out you need it or should try it?
-someone:
I had a bunch of blood tests done including a hormone panel. My testosterone and progesterone both came back at 0.
pre transition (I take estrogen) I had significantly less muscular pain after using my muscles
cavinscabin
hEDS
Yes, absolutely, without a doubt. I've been on T for 2 years now and my pain has definitely decreased since I started
MNK99
Well-Known Member
- Messages
- 5,560
POST drug syndromes are fucking krazy. i paid it forward and mentioned TEI, water fasting, the electrolyte protocol, carnivore, bodybuilding in like countless places.
FROM crazy boards to bluelight to youtube comments to reddit. SO i did my part ... WOW she had major facial changes and body changes i am sure she can get a lot better tho... but also i am sure
her docs and ppl are useless.
FROM crazy boards to bluelight to youtube comments to reddit. SO i did my part ... WOW she had major facial changes and body changes i am sure she can get a lot better tho... but also i am sure
her docs and ppl are useless.
MNK99
Well-Known Member
- Messages
- 5,560
MY EDS isn't that bad but sure autism/adhd is and ya as a male u need to make money and succeed and have all things done / set. so no sympathy or less. less from certain ppl.
so i am being too strict perhaps but still being strict is good. some mustard.. a coffee once a week isn't gonna kill you or anywhere near it. i will try no dex no coffee and just red meat and water.
better sleep early then and have been. She has serious neck brace, EDS. I had cheapo non medical brace for neck but also bought really expensive sleeves and braces everywhere else.. ankle, knee. and back.. bauersfeind neck and back ones are like 1400-2200 or 3000 dollars so ya lol. Later. not now...
AND ideally avoid that. IF i want some fucking test bc I am an athlete then I will use it and lift. IF I want dex... fine but u need minerals then outside of food. COFFEE is probably most useless to be honest and is a plant food. BUT I will try taking nothing. MAKE 10-15 days and 12 of those on nothing... 12-13 and keep going.
I Don't have severe or any psoriasis i beat excema and asthma decade(s) ago. decade and a half or more for excema but for sure being strict has benefits. for sure anxiety and depression will go.
AUTISM/ADHD .. IDK I will help it.. and tei will help more also later. I want test cream and it to work but it may not work completely anyways... for PFS. Probably will help me heds wise tho.
Perhaps later it will help PFS if I wanted or all sexual health stuff... cure all, that I can including 100% of PFS, and i can take test cream for hEDS and as a sex enhancer. BUT more importantly a life enhancer and healing/recovery/lifting enhancer. AND keeping joints strong. I think it helps hEDS which means it likely helps PFS too just not entirely.
REGARDLESS elimination... from carnivore should be stronger and so should TEI.
I think being tired as fuck is gonna be bad but I will do what I gotta. With no coffee, no dex. AND I am having no test. I guess some mustard and not fucking up is fine. NEED to stay in keto and mostly just have steaks. IT IS A COMPLETE meal. THEN AGAIN there are phytonutrients more than we expect in meats anyways, they eat plants. MORE than we can measure... so hmm. AND more than label.
BUT yeah I mean do carnivore as well as I can. 12 days prolly easy and lean again. 20 more days after that ... ripped like I nearly always have been. HOPEFULLY no depression near no anxiety. 60d after that amazing control of autism/adhd... focus and mood and thinking straight. AND the social anxiety... and tei, then keep going, and it is easy.. do that.. 3mo 6mo 10mo done but if tei does heal remaining fertility, pfs stuff good. if it does fuck all for autism month after month, quit just get more and more shredded and super aesthetic and yeah, meet girls that meet me... and who cares. use mdma for ptsd, autism.
I find it hard to believe tei does much that fasting, carnivore etc can't. BUT ev1 is different. I did like tei and did it before any carnivore but I was also younger and more optimistic made insane changes. Maybe 3-4mo from now I will be like that again. til then, this is nothing but stress mostly.

 www.ribeyerach.com
so i am being too strict perhaps but still being strict is good. some mustard.. a coffee once a week isn't gonna kill you or anywhere near it. i will try no dex no coffee and just red meat and water.
better sleep early then and have been. She has serious neck brace, EDS. I had cheapo non medical brace for neck but also bought really expensive sleeves and braces everywhere else.. ankle, knee. and back.. bauersfeind neck and back ones are like 1400-2200 or 3000 dollars so ya lol. Later. not now...
AND ideally avoid that. IF i want some fucking test bc I am an athlete then I will use it and lift. IF I want dex... fine but u need minerals then outside of food. COFFEE is probably most useless to be honest and is a plant food. BUT I will try taking nothing. MAKE 10-15 days and 12 of those on nothing... 12-13 and keep going.
I Don't have severe or any psoriasis i beat excema and asthma decade(s) ago. decade and a half or more for excema but for sure being strict has benefits. for sure anxiety and depression will go.
AUTISM/ADHD .. IDK I will help it.. and tei will help more also later. I want test cream and it to work but it may not work completely anyways... for PFS. Probably will help me heds wise tho.
Perhaps later it will help PFS if I wanted or all sexual health stuff... cure all, that I can including 100% of PFS, and i can take test cream for hEDS and as a sex enhancer. BUT more importantly a life enhancer and healing/recovery/lifting enhancer. AND keeping joints strong. I think it helps hEDS which means it likely helps PFS too just not entirely.
REGARDLESS elimination... from carnivore should be stronger and so should TEI.
I think being tired as fuck is gonna be bad but I will do what I gotta. With no coffee, no dex. AND I am having no test. I guess some mustard and not fucking up is fine. NEED to stay in keto and mostly just have steaks. IT IS A COMPLETE meal. THEN AGAIN there are phytonutrients more than we expect in meats anyways, they eat plants. MORE than we can measure... so hmm. AND more than label.
BUT yeah I mean do carnivore as well as I can. 12 days prolly easy and lean again. 20 more days after that ... ripped like I nearly always have been. HOPEFULLY no depression near no anxiety. 60d after that amazing control of autism/adhd... focus and mood and thinking straight. AND the social anxiety... and tei, then keep going, and it is easy.. do that.. 3mo 6mo 10mo done but if tei does heal remaining fertility, pfs stuff good. if it does fuck all for autism month after month, quit just get more and more shredded and super aesthetic and yeah, meet girls that meet me... and who cares. use mdma for ptsd, autism.
I find it hard to believe tei does much that fasting, carnivore etc can't. BUT ev1 is different. I did like tei and did it before any carnivore but I was also younger and more optimistic made insane changes. Maybe 3-4mo from now I will be like that again. til then, this is nothing but stress mostly.
My Experience Doing The Carnivore Diet With Ehlers-Danlos Syndrome (Over 2 Years Later)
Here's my experience with doing the carnivore diet for ehlers-danlos syndrome. It has changed my life and brought me so much healing!
www.ribeyerach.com
Last edited:
MNK99
Well-Known Member
- Messages
- 5,560
203 look ripped. mostly inflammation losing.3-4days. 7-10 33-45d i will be shredded. not 7 days but i mean 40 days ill be shredded.
more importantly anxiety, depression will be better. whether taking dex, coffee or not who cares. test cream too if i want but yes, sleeping in less pain... or slept 7 6.5-7hrs really, just had an aptmt. and hate sleeping in mostly but i will have more motivn, less anxiety no toxic anxiety, no depression in weeks. ADHD/ASD will get better.
All with carnivore
and TEI will help too.
IT is hard believing but I think it will help a lot.. and TEI will help PFS be cured, any sexual function and godwillingly also Autism (or it will be significantly reduced).
I will try not cheating at all. AND just having mustard here and there, carbonated water more... and working out a little. I was completely alpha and ripped for years to come, I was just stuck in very
bad coping mechanisms and isolated. SO If I can get rid of or make ASD less negatively impactful, that is good. I am better at trading for sure and don't wait for just big gains, protecting account is much more important. When I have 20k in memes and 20k in leverage, I will be making a lot of profit and initial investment back. That will take months tho... and I need to cash into defi, offline, and some in bank.
AND then make 30x that next year. Then this is worth it, versus law school.
Law school is way easier with HSD/hEDS being under control and no PFS. And trading is way easier too and taking days off to walk around and being open for friendship.
I kid you not, 200 people tried to be my friend probably more in 2018-2022. I really need to get rid of autism if I can. And dating will be stupidly easy. Even with ASD/ADHD it doesn't matter too too much
when you are ultraconfident, that comes from looks and health. I was only missing constant hardness and some testicle size here and there but I was beyond cured PFS.
SO add ASD, isolation, choosing to leverage trade/ being stuck in that... and the lockdown and family not understanding anything, and yeah I was getting more and more isolated. I only agreed to vax when my neck was hurt and damaged, then I gave up because I knew everyone was too stupid and I am too fast/ confusing to explain hEDS/HSD-Autism/ADHD and not wanting the vax, and trying to fix
any remaining issue of PFS, plus I couldn't admit there was still an issue when I beat everyone in terms of beating it... so.
But I will again do really well.
Have a nice weekend.
more importantly anxiety, depression will be better. whether taking dex, coffee or not who cares. test cream too if i want but yes, sleeping in less pain... or slept 7 6.5-7hrs really, just had an aptmt. and hate sleeping in mostly but i will have more motivn, less anxiety no toxic anxiety, no depression in weeks. ADHD/ASD will get better.
All with carnivore
and TEI will help too.
IT is hard believing but I think it will help a lot.. and TEI will help PFS be cured, any sexual function and godwillingly also Autism (or it will be significantly reduced).
I will try not cheating at all. AND just having mustard here and there, carbonated water more... and working out a little. I was completely alpha and ripped for years to come, I was just stuck in very
bad coping mechanisms and isolated. SO If I can get rid of or make ASD less negatively impactful, that is good. I am better at trading for sure and don't wait for just big gains, protecting account is much more important. When I have 20k in memes and 20k in leverage, I will be making a lot of profit and initial investment back. That will take months tho... and I need to cash into defi, offline, and some in bank.
AND then make 30x that next year. Then this is worth it, versus law school.
Law school is way easier with HSD/hEDS being under control and no PFS. And trading is way easier too and taking days off to walk around and being open for friendship.
I kid you not, 200 people tried to be my friend probably more in 2018-2022. I really need to get rid of autism if I can. And dating will be stupidly easy. Even with ASD/ADHD it doesn't matter too too much
when you are ultraconfident, that comes from looks and health. I was only missing constant hardness and some testicle size here and there but I was beyond cured PFS.
SO add ASD, isolation, choosing to leverage trade/ being stuck in that... and the lockdown and family not understanding anything, and yeah I was getting more and more isolated. I only agreed to vax when my neck was hurt and damaged, then I gave up because I knew everyone was too stupid and I am too fast/ confusing to explain hEDS/HSD-Autism/ADHD and not wanting the vax, and trying to fix
any remaining issue of PFS, plus I couldn't admit there was still an issue when I beat everyone in terms of beating it... so.
But I will again do really well.
Have a nice weekend.
MNK99
Well-Known Member
- Messages
- 5,560
190lb frame.. 180 185 at the time.. really it should have been around 180-190 195 if as strong as a couple yrs later, but i had pfs at the time.
they cut off <0.5lbs
if you look up loose skin you only get insane results.
if you look up marfanoid habitus you only get insane results too.
i don't have 20 deformities, no offense to these people i wish em all well. I am sure some are really smart and that they are all really tall.

they cut off <0.5lbs
if you look up loose skin you only get insane results.
if you look up marfanoid habitus you only get insane results too.
i don't have 20 deformities, no offense to these people i wish em all well. I am sure some are really smart and that they are all really tall.
MNK99
Well-Known Member
- Messages
- 5,560
I will get ripped and show my Indian zyzz pics again. I just wanted to see if the marfanoid habitus was abdomen etc or length of arms being over 1.05 ratio to height.
fucking internet.
look up PFS on propecia help... only suicide notes.
seriously internet, bad mass produced food, bad mass produced drugs (well I mean drugs that cover up symptoms, cause issues and make people take more drugs), the American and Canadian Diabetes Associations, and the like.. will mass murder 3-4bn people in 20-30yrs if they haven't already.
Go google is 6'0 6'1 an ok height... you will only find 7'0 freaks saying they're short.
go show your ripped to the bone pics on bodybuilding dot com actually they'd say mine are good
but 15 yrs before that, after realizing about loose skin, they'd be like "you need to add muscle to your frame, you're too skinny". After losing like 70lbs and adding like 25-35lbs, now it is 50lbs.. gear and training hard 55lbs 60lbs, only training hard 50lbs extra muscle.
if you're a kid: "am i gay?" all just trans porn shows up.
if you are a kid and you search: "will i ever lose weight, cure x condition, etc?" --> no you'll die, go to the doctor, take their drugs, go get a sex change.
I guarantee you the internet will end mankind.
fucking internet.
look up PFS on propecia help... only suicide notes.
seriously internet, bad mass produced food, bad mass produced drugs (well I mean drugs that cover up symptoms, cause issues and make people take more drugs), the American and Canadian Diabetes Associations, and the like.. will mass murder 3-4bn people in 20-30yrs if they haven't already.
Go google is 6'0 6'1 an ok height... you will only find 7'0 freaks saying they're short.
go show your ripped to the bone pics on bodybuilding dot com actually they'd say mine are good
but 15 yrs before that, after realizing about loose skin, they'd be like "you need to add muscle to your frame, you're too skinny". After losing like 70lbs and adding like 25-35lbs, now it is 50lbs.. gear and training hard 55lbs 60lbs, only training hard 50lbs extra muscle.
if you're a kid: "am i gay?" all just trans porn shows up.
if you are a kid and you search: "will i ever lose weight, cure x condition, etc?" --> no you'll die, go to the doctor, take their drugs, go get a sex change.
I guarantee you the internet will end mankind.
MNK99
Well-Known Member
- Messages
- 5,560
Go try and google: "typical fat woman", "fat white trash woman", "ugly fat short covid nurse", all you get is psy-ops.
Sick and tired of the goddamned west and their big tech manipulations. PEOPLE can go suck off GMO cows and bulls and add carageenan to their yogurts and add cellulose (wood/ saw dust probably, plant material for sure) to their stupid pre shredded cheese.
Look around 98-99% of people have subhuman intellect.
You would think the fucking Wuhan Plague would have killed more of these disgusting fat monsters, but no.
Sick and tired of the goddamned west and their big tech manipulations. PEOPLE can go suck off GMO cows and bulls and add carageenan to their yogurts and add cellulose (wood/ saw dust probably, plant material for sure) to their stupid pre shredded cheese.
Look around 98-99% of people have subhuman intellect.
You would think the fucking Wuhan Plague would have killed more of these disgusting fat monsters, but no.
MNK99
Well-Known Member
- Messages
- 5,560
How could the social justice cucks that work at postal office (0/10) dare think they have dominian over me???
I will make 10-18mn usd one year, and it won't be this or next yr most likely. and then one year 200mn and I will buy an island and hunt people for sport.
IF people weren't disgusting animals, and had nutrition. I would eat them. But I don't eat vegans or brainlets.
I will make 10-18mn usd one year, and it won't be this or next yr most likely. and then one year 200mn and I will buy an island and hunt people for sport.
IF people weren't disgusting animals, and had nutrition. I would eat them. But I don't eat vegans or brainlets.